Blog

  • Urinary Hesitancy: Causes, Symptoms, & Treatments

    Urinary Hesitancy: Causes, Symptoms, & Treatments

    Urinary hesitancy, the difficulty, delay, or interruption in starting urination, can be a frustrating and unsettling experience. 

    What should be an automatic bodily function becomes a source of stress and anxiety. Simple bathroom visits can become stressful and frustrating when your body doesn’t respond as expected.

    Many people find themselves planning activities around bathroom access or feeling isolated and worried about their symptoms.

    However, in most cases, targeted pelvic floor exercises, gentle stretching, medications, and lifestyle modifications can support healthy bladder function and improve urine flow.

    In this guide, we will explore the causes, symptoms, and potential complications of urinary hesitancy, as well as diagnosis and treatment options to help you manage symptoms and regain confidence in your daily life.
    What is Urinary Hesitancy?

    Urinary hesitancy is the difficulty initiating or maintaining a steady stream of urine despite the urge to void.

    It’s more than just a minor inconvenience; it’s a disruption of a fundamental process. It often occurs alongside other symptoms like a weak stream, straining, or a sensation of incomplete emptying.

    What does urinary hesitancy feel like?

    Patients describe it as:

    • A frustrating “hold-up” where you feel ready, but your body doesn’t cooperate.
    • Needing to concentrate or wait several seconds to a minute for the flow to begin.
    • A stop-and-start pattern during urination.
    • The need to apply abdominal pressure or strain to get started.
    • An underlying feeling that you haven’t fully emptied your bladder, even after finishing.

    What are the Causes of Urinary Hesitancy?

    Hesitancy is a symptom, not a disease itself. It signals an obstruction, a neurological issue, or weakened muscles. Causes often differ by biological sex due to anatomical differences.

    Causes of Urinary Hesitancy in Females

    • Pelvic Organ Prolapse: When the bladder, uterus, or rectum descends into the vaginal canal, it can alter the urethra’s angle and function.
    • Urinary Tract Infections (UTIs): Inflammation and swelling in the urinary tract can cause hesitation and pain.
    • Post-Surgical Effects: Scar tissue or nerve damage following pelvic or back surgeries (e.g., hysterectomy, spinal surgery).
    • Pelvic Floor Dysfunction: Overactive or tight pelvic floor muscles (not just weak ones) can prevent the urethral sphincter from relaxing properly to allow urine out.

    A study of female patients found that a continuous detrusor voiding pressure curve and a prolonged, “tailed” shape on the free urine flow curve were strongly associated with bladder outlet obstruction (BOO).

    Causes of Urinary Hesitancy in Males

    • Benign Prostatic Hyperplasia (BPH): The most common cause in men over 50. An enlarged prostate gland constricts the urethra, acting like a kink in a garden hose.
    • Prostatitis: Inflammation or infection of the prostate gland, causing swelling and irritation.
    • Urethral Stricture: Scarring that narrows the urethra, often from past injury, infection, or medical procedures.
    • Prostate Cancer: While less common, it can cause similar obstructive symptoms.

    A clinical study examined nearly 500 men with BPH and found that symptoms such as weak urinary stream and hesitancy are among the most common and bothersome components of BPH-related Lower urinary tract symptoms (LUTS).
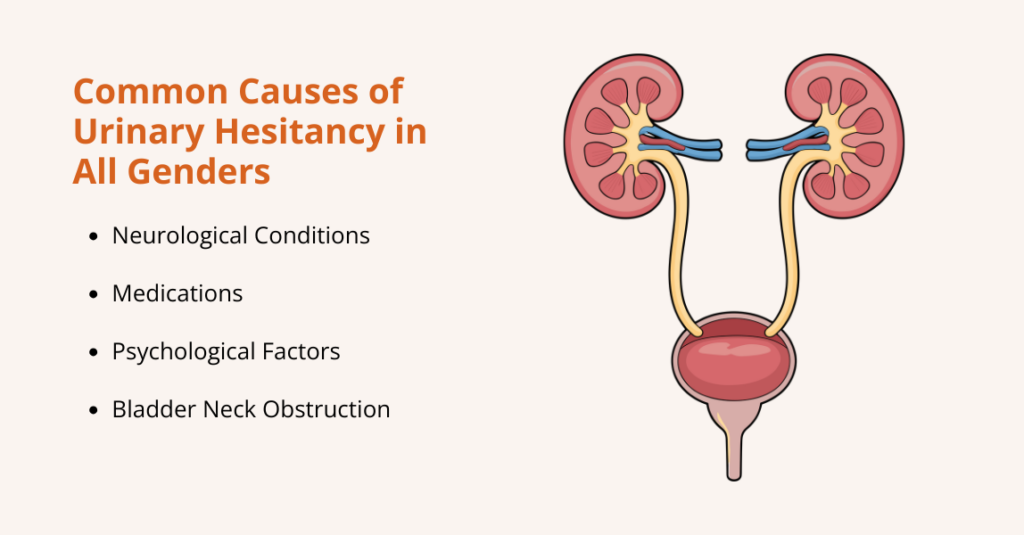
    Common Causes in All Genders:

    • Neurological Conditions: Diseases that disrupt nerve signals between the brain and bladder (e.g., Multiple Sclerosis, Parkinson’s, Stroke, Spinal Cord Injuries, Diabetes-induced neuropathy).
    • Medications: Side effects of common drugs like antihistamines, decongestants, anticholinergics, tricyclic antidepressants, and certain muscle relaxants.
    • Psychological Factors: Extreme anxiety, “shy bladder” syndrome (paruresis), or a history of trauma.
    • Bladder Neck Obstruction: A malfunction of the muscles at the bladder’s outlet.
    What are the Symptoms of Urinary Hesitancy?

    Hesitancy rarely occurs in isolation. Look for these accompanying signs:

    • Weak or intermittent urine stream
    • Straining to urinate
    • Feeling of incomplete bladder emptying
    • Dribbling at the end of urination
    • Increased time needed to urinate
    • Lower abdominal discomfort or fullness

    What are the Risk Factors for Urinary Hesitancy?

    Urinary hesitancy does not usually happen without a reason. Certain health conditions, lifestyle factors, and medications can increase the risk of having trouble starting urination.

    Age-Related Changes

    As people age, the muscles that control the bladder and urethra may weaken or lose coordination. This can slow urine flow and make it harder to start urinating.

    • More common in adults over 50
    • Often develops gradually

    Prostate-Related Conditions (in men)

    An enlarged prostate is one of the most common risk factors for urinary hesitancy.

    Neurological Conditions

    The bladder depends on proper nerve signals to function normally. Any condition that affects these signals can cause hesitancy.

    • Diabetes-related nerve damage
    • Parkinson’s disease
    • Multiple sclerosis
    • Stroke or spinal cord injury

    Psychological Factors

    In some cases, mental or emotional factors play a role.

    • Anxiety or stress
    • Habitually holding urine for long periods
    • Difficulty urinating in public settings

    Medications

    Some medications interfere with bladder muscle contraction or tighten the urinary sphincter. Common examples include:

    • Antihistamines and cold medications
    • Decongestants
    • Certain antidepressants
    • Opioid pain medications

    Other Key Factors

    Several additional conditions can also interfere with normal urine flow. 

    For example, urinary tract infections and inflammation, such as UTIs, prostatitis, or urethritis, can cause swelling and irritation that temporarily narrow the urinary passage.

    Similarly, pelvic floor disorders, including pelvic organ prolapse, childbirth-related muscle strain, or chronic pelvic muscle tension, may disrupt the coordination needed to start urination.

    In other cases, structural blockages, such as urethral strictures, bladder or kidney stones, pelvic tumors, or scar tissue from previous surgery or injury, can physically obstruct urine flow.

    In addition, severe or long-term constipation can place pressure on the bladder and urethra, making it harder to begin urinating.

    What are the Complications of Urinary Hesitancy?

    When urine stays in the bladder, er it creates problems: bacteria can grow, the bladder can overstretch or weaken, and pressure can back up into the kidneys. Left untreated, these changes can progress.

    Common complications of urinary hesitancy include:

    • Recurrent urinary tract infections (UTIs)
    • Acute or chronic urinary retention
    • Bladder overdistension and detrusor (muscle) damage
    • Bladder stones (calculi)
    • Overflow incontinence
    • Hydronephrosis and kidney injury
    • Bladder diverticula and structural changes
    • Sepsis (rare but serious)

    If urinary hesitancy is new, progressive, painful, or accompanied by fever or reduced urine output, seek medical evaluation. Prompt treatment of retention or infection prevents most of these complications.

    How Do Doctors Test for Urinary Hesitancy?

    Urinary hesitancy is usually diagnosed by a primary care physician (PCP) or healthcare provider.

    Initial Assessment

    The evaluation begins with a detailed discussion of your symptoms, a review of your medical history, and a physical examination.

    During this visit, your provider may ask questions such as:

    • How long have you had difficulty starting urination?
    • Has your urine stream become weaker than usual?
    • Did the symptoms develop gradually or start suddenly?
    • Are you taking any prescription or over-the-counter medications?
    • Do your symptoms worsen after certain activities or after consuming specific foods or drinks?

    These questions help identify possible causes and guide further testing.

    Tests Used to Diagnose Urinary Hesitancy

    If needed, your healthcare provider may order tests to confirm the diagnosis and determine the underlying cause.

    Urodynamic Testing

    Urodynamic tests measure how well your bladder and urethra store and release urine. These tests can assess:

    • The amount of urine you pass
    • The speed and strength of your urine stream
    • Pressure within the bladder during filling and emptying

    Additional Diagnostic Tests

    Depending on your symptoms, your provider may also recommend:

    • Imaging tests, such as an ultrasound or CT scan, are used to evaluate bladder emptying and check prostate size
    • Cystoscopy, which uses a small camera to look inside the urethra and bladder
    • Digital rectal exam, to assess prostate size and detect abnormalities
    • Urinalysis, to examine urine for signs of infection, blood, or other abnormalities
    • Urine culture, to identify bacterial infections

    Together, these evaluations help determine the cause of urinary hesitancy and guide appropriate treatment.
    Treatment for Urinary Hesitancy

    Treatment for urinary hesitancy depends on the underlying cause and any other comorbidities. Your healthcare provider may recommend

    • Home Remedies
    • Bladder Retraining (Timed Voiding)
    • Pelvic Floor Physical Therapy
    • Medications
    • Surgery & Procedures
    • Sacral Nerve Stimulation (Sacral Neuromodulation)

    Home Remedies

    Some cases of urinary hesitancy can improve with safe home strategies, but always consult your provider first:

    • Heat: Applying a heating pad, using a hot water bottle, or taking a warm shower/bath can relax the pelvic muscles.
    • Gentle abdominal massage: Light pressure near the bladder while peeing may help strengthen the stream.
    • Bowel regulation: Using stool softeners or adjusting diet to prevent constipation can reduce pressure on the bladder.
    • Bladder diary: Track fluid intake, urine volume, stream strength, time to urinate, frequency, and other symptoms to help your provider monitor progress and adjust treatment.

    Bladder Retraining (Timed Voiding)

    Bladder retraining involves voiding at set intervals, typically every 2 hours, to prevent overfilling of the bladder.

    You do this even if you don’t feel the urge to urinate. Over time, it helps improve bladder control and ease hesitancy.

    Pelvic Floor Physical Therapy

    Pelvic floor physical therapy (PT) is an effective way to treat urinary hesitancy caused by tight or uncoordinated pelvic floor muscles.

    These muscles need to contract and fully relax to allow normal urination. If the muscles remain tense, go into spasm, or cannot relax properly, it can lead to urinary hesitancy and other bladder symptoms.

    Targeted exercises help stretch and relax the pelvic floor muscles, improving urine flow. You can perform some exercises at home, but working with a physical therapist ensures personalized guidance.

    Medications

    Depending on the cause, your provider may prescribe:

    • Alpha-blockers to relax muscles in the bladder and prostate
    • 5-alpha-reductase inhibitors (like dutasteride or finasteride) to shrink the prostate
    • Antibiotics to treat urinary tract infections

    Surgery & Procedures

    Surgery is considered when medications, physical therapy, or less invasive treatments are not effective. Common surgical options include:

    • Prostate surgery (partial prostatectomy or transurethral resection of the prostate) to remove excess prostate tissue and relieve BPH-related obstruction.
    • Pelvic organ prolapse repair to restore support to dropped organs, reducing pressure on the bladder and improving urination.

    In addition, minimally invasive procedures can improve urine flow without major surgery:

    • Urethral dilation or reconstruction for a narrow or obstructed urethra.
    • Prostatic Artery Embolization (PAE), a non-surgical procedure for BPH, reduces blood flow to the enlarged prostate, shrinking it and relieving urinary symptoms.

    Sacral Nerve Stimulation (Sacral Neuromodulation)

    A small device is implanted near the upper buttock. It sends mild electrical impulses to the sacral nerve, helping stimulate bladder muscles and improve urine flow.

    Frequently Asked Questions (FAQs)

    What is the difference between urinary hesitancy and urinary retention?

    Urinary hesitancy and urinary retention are related but distinct problems in the urinary process. Urinary hesitancy refers specifically to the difficulty or delay in initiating the flow of urine once you feel the urge to go; it’s about a troublesome start, often accompanied by straining or a weak stream, but you usually can eventually urinate. Urinary retention, on the other hand, is the more severe condition where the bladder cannot empty properly, meaning little or no urine is released despite an urge, often leading to painful bladder distention and the potential for serious complications.

    Why does it feel like I have to pee, but nothing comes out?

    This sensation is often caused by urinary hesitancy or incomplete bladder emptying. Even though your bladder signals the need to urinate, several factors can prevent urine from flowing normally:

    • Weak bladder muscle contractions (detrusor underactivity): The bladder isn’t squeezing strongly enough to push urine out.
    • Obstruction in the urinary tract: In men, an enlarged prostate (BPH) can block the urethra; in women, pelvic organ prolapse or urethral narrowing can have a similar effect.
    • Tight or uncoordinated pelvic floor muscles: If the muscles around the bladder and urethra remain tense, they can prevent urine from starting or fully flowing.
    • Nerve or neurological issues: Conditions such as diabetes, multiple sclerosis, or spinal injuries can interfere with the signals between the bladder and brain.
    • Infections or inflammation: Swelling from a urinary tract infection or urethritis can make it difficult for urine to pass.

    If you experience this frequently, feel discomfort, or cannot urinate at all, it’s important to seek medical evaluation. 

    When should someone seek medical care for urinary hesitancy?

    You should seek medical evaluation for urinary hesitancy if:

    • Your symptoms suddenly appear or get worse over time.
    • You experience pain, burning, or discomfort while urinating.
    • There is blood in your urine or unusual discharge.
    • You are unable to urinate at all.
    • You have fever, nausea, or lower back/flank pain, which could indicate an infection or kidney problem.

    Even if your symptoms are mild, persistent urinary hesitancy should be discussed with a healthcare provider to identify the cause and prevent complications.

    How can urinary hesitancy be prevented?

    You can help prevent urinary hesitancy through healthy bladder habits, such as going to the bathroom regularly and avoiding holding urine for long periods. Staying hydrated and managing constipation can reduce pressure on the bladder and urethra, while pelvic floor exercises help maintain muscle strength and proper coordination. Additionally, promptly addressing urinary tract infections, prostate issues, or other underlying conditions can lower the risk of complications that contribute to hesitancy.

    What is the most common treatment for urinary retention?

    The most common initial treatment for urinary retention is catheterization, which temporarily drains urine from the bladder to relieve discomfort and prevent complications. Depending on the cause, healthcare providers may also recommend medications (such as alpha-blockers for men with prostate enlargement), pelvic floor therapy, or surgical procedures to address obstructions or improve bladder function. However, the exact approach depends on whether the retention is acute (sudden) or chronic (long-term), as well as on the underlying cause.

    What medication is used for urinary hesitancy?

    The medication prescribed for urinary hesitancy depends on the underlying cause:

    • Alpha-blockers (e.g., tamsulosin, alfuzosin) help relax the muscles in the bladder neck and prostate, thereby improving urine flow, and are commonly used for men with benign prostatic hyperplasia (BPH).
    • 5-alpha-reductase inhibitors (e.g., finasteride, dutasteride) may be prescribed to shrink an enlarged prostate over time.
    • Antibiotics are used if urinary tract infections contribute to hesitancy.

    Always consult a healthcare provider before starting any medication, as the choice depends on your specific condition, other health factors, and potential side effects.

    How many seconds is urinary hesitancy?

    There isn’t a strict “number of seconds” that defines urinary hesitancy, because it varies by person and by the underlying cause. Research suggests that a delay of over 11.3 seconds after attempting to urinate may be considered significant, especially if it happens repeatedly or is accompanied by other symptoms like a weak stream, straining, or incomplete emptying.

    Conclusion

    The journey with urinary hesitancy is more than physical; it’s an emotional drain that can make you feel like your body is working against you.

    The constant anticipation, the planning, the silent worry, it’s a heavy load to carry alone. But please understand this: Your struggle is valid, and it is treatable.

    With appropriate evaluation, targeted therapies, lifestyle modifications, and, in some cases, medical or surgical interventions, most people can achieve meaningful improvement.

    Small changes, guided exercises, and professional support can help restore confidence, reduce frustration, and allow you to reclaim control over daily routines.

    Remember, seeking help is the first step toward relief. You don’t have to navigate urinary hesitancy alone; support, treatment, and better bladder health are within reach.


  • Stiff Knee: Causes, Symptoms, and Treatments

    Stiff Knee: Causes, Symptoms, and Treatments

    A stiff knee is a very common problem that can happen to anyone.

    For some, it may develop after physical activity or overuse, while for others, especially older adults, it can be linked to natural wear and tear in the knee joint.

    When your knee feels stiff, you may find it hard to bend or straighten it fully. This limited movement is often accompanied by discomfort or pain, which can make everyday activities such as walking, standing, or climbing stairs difficult and frustrating. 

    While occasional stiffness might be a minor inconvenience, persistent symptoms can signal an underlying issue requiring attention. Ignoring these symptoms may allow the condition to worsen over time.

    In this post, we explain what a stiff knee really means, explore the possible causes and warning signs, and discuss treatments you can try at home as well as professional care options.

    What is a Stiff Knee?

    A stiff knee is a sensation of tightness or resistance in the knee joint that limits normal movement.

    You may find it hard to fully straighten (extend) or bend (flex) your knee. This stiffness can be accompanied by pain, swelling, or a feeling of “locking.”

    It’s not a diagnosis itself but rather a symptom of various conditions affecting the joint’s structures, including bones, cartilage, ligaments, tendons, or the joint lining.

    For example, if a meniscus cartilage is torn or a ligament is stretched, you might feel the knee locking or catching and unable to straighten. Likewise, arthritis causes swelling of the joint surfaces, making movement feel painful and limited.

    What are the Causes of a Stiff Knee?

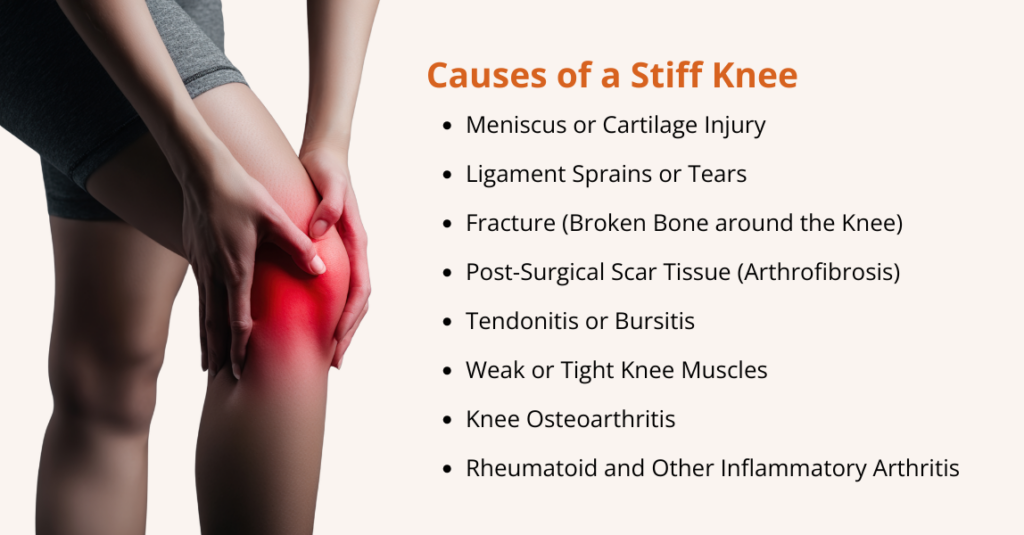
    Knee stiffness can arise from a variety of causes, including injuries, wear and tear, inflammation, and infection. Potential causes of knee stifness include:

    Meniscus or Cartilage Injury

    The menisci are C-shaped cushions of cartilage between the thighbone and shinbone. A sudden twist or fall can tear a meniscus, or age-related wear can weaken it.

    When the meniscus tears, the knee often locks or becomes stiff because the torn fragment blocks motion. Patients may hear or feel a pop when it tears, then notice:

    • Pain and swelling around the knee
    • Locking or catching, inability to fully straighten the knee
    • Loss of motion and a feeling that the knee might give way

    Even if you can still walk, the knee may feel stiff or stuck. Torn cartilage is a common cause of acute stiffness, and it often requires imaging or a doctor’s exam for diagnosis.

    Ligament Sprains or Tears

    Ligaments are strong bands that connect the knee bones. A sudden twist, impact, or hyperextension can sprain or tear a ligament.

    This usually causes immediate pain and swelling, which in turn makes the knee stiff. You might also feel the knee is unstable or weak. Common signs include:

    • Knee pain and swelling shortly after the injury
    • Instability, like a sensation that the knee may buckle or give out
    • Limited motion and difficulty bending or straightening the knee fully.

    For example, an anterior cruciate ligament (ACL) tear often causes rapid swelling (hemarthrosis) and a sensation of the knee locking in place. Like a torn meniscus, a torn ligament usually causes stiffness until it heals or is repaired.

    Fracture (Broken Bone around the Knee)

    A bone fracture in or near the knee (such as a broken kneecap, tibia, or femur) makes the knee very stiff. The fracture causes severe pain, swelling, and, in many cases, a visible deformity, thereby preventing normal knee movement.

    Symptoms of a knee-area fracture include:

    • Severe pain, especially with any weight on the leg
    • Swelling and bruising around the knee
    • Tenderness and deformity (the knee may look “out of place” or bent)

    Because a fracture is an emergency, it must be treated right away (often with immobilization or surgery). Without proper alignment, broken pieces will keep the knee locked and stiff.

    Post-Surgical Scar Tissue (Arthrofibrosis)

    Sometimes, after surgery (or a bad injury), the knee heals with too much scar tissue in the joint. This condition, called arthrofibrosis or “stiff knee syndrome,” literally glues down the joint.

    Excess scar tissue makes bending or straightening the knee very difficult. People with arthrofibrosis typically have:

    • Progressively worsening pain and stiffness after surgery
    • Swelling and a feeling of heat in the knee
    • Difficulty fully extending the knee (often the leg stays slightly bent)

    Research shows that about 2–35% of patients develop arthrofibrosis after major knee operations like ACL reconstruction or joint replacement.

    Tendonitis or Bursitis

    Overuse or irritation of knee tendons and bursae can also cause stiffness. For example, patellar tendonitis (“jumper’s knee”) inflames the tendon below the kneecap.

    Likewise, bursitis inflames a fluid-filled sac (bursa) in the knee (often in front of or inside the knee). Both lead to swelling and pain that limit motion. Typical features include:

    • Patellar (knee) tendonitis: Pain and tenderness at the front of the knee, especially just below the kneecap.
    • Knee bursitis: Painful swelling over a bony point of the knee. The area often feels warm, tender, and swollen, and knee movement may be painful or limited.

    In both cases, inflammation makes the joint feel tight and usually worsens with activity (e.g, jumping or climbing stairs).

    Weak or Tight Knee Muscles

    The muscles around your knee, especially the quadriceps (front of the thigh) and hamstrings (back of the thigh), play a key role in supporting and stabilizing the joint.

    If these muscles are weak, the knee can move less smoothly and may be more prone to injury. On the other hand, if the muscles are very tight, they can pull on the joint unevenly, limiting motion and making the knee feel stiff.

    Research has shown that tight quadriceps muscles can increase stress on the knee joint and may contribute to the development of osteoarthritis over time.

    Knee Osteoarthritis

    Osteoarthritis (OA) is the most common reason for long-term knee stiffness. In OA, the cartilage cushioning the joint gradually wears away.

    As the cartilage thins, bone rubs on bone, and small bony spurs (osteophytes) can grow. This leads to chronic pain, swelling, and stiffness. As a result, individuals often notice stiffness when rising from a seated position or upon waking.

    Rheumatoid and Other Inflammatory Arthritis

    Autoimmune arthritis (like rheumatoid arthritis, psoriatic arthritis, or lupus) attacks the knee’s lining (synovium) and causes chronic inflammation.

    In rheumatoid arthritis (RA), for example, the immune system inflames the joint lining, leading to swelling, warmth, and pain. This inflammation causes the knee to become extremely stiff, particularly in the morning or after rest, resulting in:

    • Swollen knee
    • Warm joints
    • Persistent stiffness
    • Fluctuating pain

    Other inflammatory diseases, such as gout or pseudogout (see below), similarly cause episodes of sudden pain and stiffness. Overall, any form of chronic arthritis means ongoing joint swelling that leads to limited motion and stiffness.

    What are the Symptoms of a Stiff Knee?

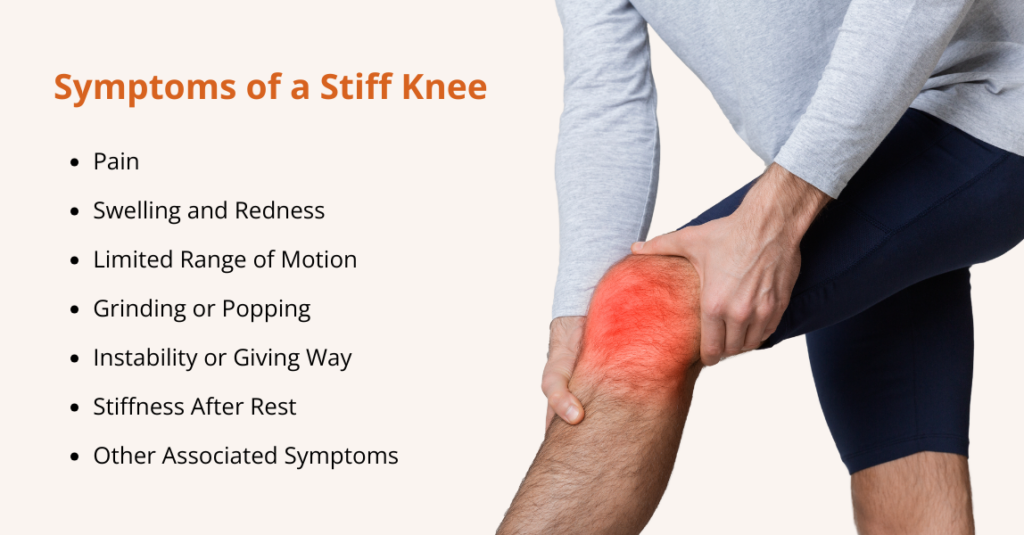
    A stiff knee often comes with other symptoms. These may include:

    • Pain: You may feel aching, burning or stabbing pain in the knee. Bel Marra Health notes that a stiff knee often brings sharp or aching pain, especially when moving.
    • Swelling and Redness: Inflammation often causes the knee to swell. Warmth and redness can occur if there is active inflammation or infection.
    • Limited Range of Motion: You might not be able to fully bend or straighten the knee. The joint may feel locked or catch at certain angles. 
    • Grinding or Popping: You may hear or feel noises in the knee, such as creaking, clicking or grinding sounds (called crepitus) when moving an arthritic knee.
    • Instability or Giving Way: The knee may feel weak or buckle under weight. Ligament injuries or advanced arthritis can make the knee unstable.
    • Stiffness After Rest: Knees with arthritis or inactivity may feel especially stiff after sitting or sleeping. It often eases with light movement
    • Other Associated Symptoms: Other symptoms like fever, severe pain at rest, or knee deformity are less common but important red flags.

    Importantly, a key point is that stiffness often comes with some pain or swelling, though the knee may not always be very painful.

    Treatments for Stiff Knees

    The most suitable treatment for knee stiffness depends on the cause and severity. Mild stiffness often improves with home care, while persistent or severe cases may need medical treatments.

    At-Home Care

    For many people, simple home remedies can significantly ease knee stiffness:

    • RICE/PRICE

    Rest the knee to avoid further strain. Apply Ice packs for 10–20 minutes several times a day to reduce swelling. Use Compression (an elastic bandage or sleeve) to support the knee and minimize swelling.

    Elevate the leg on pillows to help drain fluid. The “PRICE” principle (Protect, Rest, Ice, Compress, Elevate) is often recommended for early stiffness relief.

    • Gentle Exercise & Stretching

    Once acute pain subsides, gentle motion helps keep the knee flexible. Strengthening the muscles around the knee (quadriceps, hamstrings) can reduce stress on the joint.

    For example, straight-leg raises, hamstring curls, and half-squats (within a pain-free range) build support for the knee. Stretches like heel slides, calf stretches, and using a strap for assisted knee stretches improve range of motion.

    Low-impact cardio (walking, swimming, cycling) keeps joints moving without jarring them. 

    • Heat and Cold Therapy

    Cold packs (cryotherapy) can numb pain and reduce inflammation. You can also use heat (warm bath or heating pad) to relax tight muscles before activity.

    For example, using heat before exercise and icing afterward is a common strategy.

    • Supportive Devices

    A knee brace or compression sleeve can help stabilize the knee and prevent movements that worsen stiffness. Even taping the knee or using a simple bandage can offer support during recovery.

    • Self-Massage

    Gently massaging the muscles around the knee (quads, hamstrings) can improve circulation and relieve tightness. Some people also use topical ointments (menthol, capsaicin creams) for temporary relief, although these effects are mild.

    Lifestyle Changes

    Adjusting daily habits can help relieve chronic stiffness and prevent flare-ups:

    • Maintain a Healthy Weight

    Excess weight puts extra load on the knees. Losing even a small amount of weight can reduce pressure and stiffness in the knee joint.

    Research shows that weight loss can significantly reduce knee stiffness and pain. Even modest weight reduction improves symptoms. 

    For every 1% of body weight lost, knee pain, stiffness, and physical function scores improve by about 2%. Larger weight loss leads to even greater benefits.

    • Anti-Inflammatory Diet

    A balanced diet rich in fruits, vegetables, whole grains, and omega-3 fats (fish oil, walnuts) can help control inflammation.

    If gout is the issue, limiting red meat, alcohol, and sugary drinks can lower uric acid levels and reduce knee flares.

    • Regular Low-Impact Exercise

    Incorporate joint-friendly exercise into your routine. Water aerobics, cycling, or walking on soft surfaces strengthen knee muscles without jarring the joints.

    • Avoid Prolonged Inactivity

    Don’t stay seated or standing still for too long. If you have a desk job or long drives, take breaks to stand, walk, and gently bend your knees.

    • Proper Footwear and Support

    Wear shoes with good arch support and cushioning. Avoid high heels or unsupportive shoes that can alter your knee alignment. In some cases, orthotic inserts or a cane (to offload the knee) can help.

    • Practice Good Posture

    When walking or exercising, use proper form. Strong hip and core muscles take some burden off your knees.

    • Quit Smoking

    While not a direct cause of knee stiffness, smoking impairs blood flow and slows healing, which can make recovery from knee problems harder.

    By making these lifestyle changes, you can minimize factors that contribute to knee stress and stiffness.

    Professional Treatments

    If stiffness persists or is severe, medical intervention may be needed.

    • Medical Evaluation

    A doctor will take a history (how the knee stiffened, what aggravates it) and perform a physical exam. Also, they may order imaging tests (X-ray, MRI) to look for arthritis, fractures, ligament tears, or meniscus injuries.

    • Physical Therapy

    A physical therapist can design a personalized exercise program to increase knee flexibility and strength. PT is often the first-line professional treatment for stiffness.

    Exercises may include guided range-of-motion stretches, strengthening routines, balance training, and manual therapy.

    • Medications

    In addition to OTC drugs, doctors can prescribe stronger anti-inflammatories, pain relievers, or muscle relaxants if needed.

    • Corticosteroid Injections

    For many kinds of knee inflammation (arthritis flare, bursitis), injecting a corticosteroid into the knee joint can dramatically reduce swelling and stiffness for weeks to months.

    • Viscosupplementation

    In osteoarthritis, injections of hyaluronic acid derivatives (gel) can sometimes improve lubrication in the joint and reduce stiffness, though results vary.

    • Knee Bracing and Orthotics

    A doctor or therapist can fit you for a specialized knee brace or orthotic insert (shoe insert) to realign or relieve the joint.

    • Surgery

    If conservative treatments fail, possible procedures include arthroscopic surgery to trim torn meniscus or remove scar tissue, ligament reconstruction (e.g. ACL repair), or knee replacement for advanced arthritis.

    The most suitable treatment for knee stiffness depends entirely on the cause and severity. That is why a doctor’s evaluation is important if home remedies don’t help or symptoms worsen.

    Frequently Asked Questions (FAQs)

    Why does my knee feel stiff?

    Your knee feels stiff because something is interfering with the normal, smooth mechanics of the joint. Stiffness occurs when the hinge becomes swollen, tight, or lacks adequate support.

    Here’s why that might be happening:

    • Inflammation and Swelling: Whether from an injury (such as a sprain or tear) or arthritis, inflammation causes fluid and swelling within the joint. This physically limits space and makes movement difficult and stiff.
    • Muscle Weakness or Tightness: Weak muscles, especially in the thighs, fail to stabilize the joint properly. Tight muscles in the hips or legs can also pull on the knee, causing stiffness and restricting motion.
    • Structural Changes: Conditions like osteoarthritis wear down the smooth cartilage that cushions your knee. This can lead to bone spurs and joint space loss, resulting in stiff, gritty movement.
    • Weight and Pressure: Carrying extra weight places significantly more pressure on the knees with each step, which can accelerate wear and contribute to stiffness.

    For example, after sitting for a while, fluid can settle in the knee, and your muscles cool down, making the joint feel stiff until you move. 

    Is walking good for a stiff knee?

    Generally, yes, walking is a gentle, low-impact exercise that can actually help a stiff knee. Moving the knee promotes circulation and lubricates the joint, which can reduce stiffness over time. However, start slowly and stop if walking causes sharp pain. If weight-bearing is painful, you might use walking aids or perform exercises in a pool until the knee gets stronger.

    Does knee stiffness ever go away?

    Yes, knee stiffness can go away, but it depends on the underlying cause. In many cases, stiffness caused by minor injuries, muscle tightness, overuse, or temporary inflammation improves with rest, gentle movement, stretching, and proper treatment. 

    Can you reverse stiff knees?

    In some cases, stiff knees can be reversed, but it depends on what is causing the stiffness. When stiffness is due to muscle tightness, weakness, minor injuries, or inflammation, it can often be improved, or even fully reversed, with targeted exercises, stretching, physical therapy, and lifestyle changes such as weight management. However, if stiffness is caused by long-term joint damage, such as advanced osteoarthritis, the structural changes cannot be completely reversed.

    When to see a Doctor for a stiff knee?

    You should see a doctor for a stiff knee if you notice any of the following:

    • Knee stiffness that lasts more than a few days or continues to worsen
    • Severe or persistent knee pain that does not improve with rest
    • Significant swelling, redness, or warmth around the knee
    • Inability to fully bend or straighten the knee
    • The knee locks, catches, or feels stuck during movement
    • The knee gives way or feels unstable when walking or standing
    • Stiffness following a fall, twist, or direct injury to the knee
    • Fever or signs of infection along with knee pain or swelling

    Seeking medical care early can help identify the cause of knee stiffness and prevent further joint damage.

    Conclusion

    Knee stiffness can be a source of worry and discomfort, but understanding its causes and treatments can help you regain movement.

    Stiffness most often comes from injuries or arthritis, which inflame the joint and limit motion.

    Thankfully, many cases can be relieved with simple measures: resting, applying ice, taking anti-inflammatories, and doing gentle exercises will often reduce stiffness

    Also, lifestyle changes like weight control and low-impact exercise further aid recovery.

    Listen to your body: if home remedies aren’t enough or warning signs appear, see a doctor for help in keeping your knees healthy and pain-free.

    With the right care you can often work past stiffness to move more freely.

  • Heavy Menstrual Bleeding Explained: Causes, Symptoms & Solutions

    Heavy Menstrual Bleeding Explained: Causes, Symptoms & Solutions

    Periods are a normal part of life, but they shouldn’t dominate it.

    Many people silently endure heavy menstrual bleeding, feeling embarrassed or believing it’s just their “normal.”

    Yet this condition can drain energy, disrupt work or family life, and lead to anemia and other health problems.

    Importantly, heavy periods also stir emotions, fear of leaking in public, cancelling social plans, or worrying about possible health issues. Your struggle is valid, and compassionate care exists.

    In this post, we’ll walk you through what heavy periods are, why they happen, and the steps you can take to regain control and feel like yourself again.

    What is Heavy Menstrual Bleeding?

    Heavy menstrual bleeding, also called menorrhagia, happens when your period is much heavier than normal or lasts longer than seven days.

    If heavy or prolonged bleeding isn’t treated, it can start to affect your everyday life and make it hard to do normal activities. It can also lead to anemia, a common blood condition that may cause fatigue, weakness, or low energy.

    Also, constantly layering pads, worrying about leaks, and staying home because of heavy bleeding can feel exhausting and overwhelming.

    In some cases, ongoing heavy bleeding may be linked to other underlying health problems that need medical care.

    Common Causes of Heavy Menstrual Bleeding

    Menorrhagia can stem from multiple factors; sometimes the cause is unknown. Common categories include:

    Hormonal Imbalances

    Estrogen and progesterone control the uterine lining. Imbalances from obesity, insulin resistance, thyroid disease, or polycystic ovary syndrome (PCOS) can thicken the lining and lead to heavy bleeding. Anovulation (when the ovaries don’t release an egg) is another cause.

    Noncancerous Growths

    Uterine fibroids (benign muscle tumors), polyps, and adenomyosis (endometrial tissue growing into the uterine muscle) increase blood loss. Fibroids can distort the uterus and cause sudden gushes of blood during periods.

    Infections and Inflammation

    Sex ually transmitted infections such as trichomoniasis, gonorrhea, and chlamydia, or chronic endometritis, can trigger heavy bleeding.

    Pregnancy Complications

    Miscarriage, ectopic pregnancy, or a cesarean scar (“C‑section niche”) may present as unexpected heavy bleeding.

    Bleeding Disorders

    Von Willebrand disease, platelet function disorders, and other genetic bleeding disorders impair clotting. These often go undiagnosed but should be considered when menstrual bleeding is severe.

    Medications

    Blood thinners (e.g., warfarin, apixaban, rivaroxaban), aspirin, and certain hormonal therapies can increase blood flow.

    Other Medical Conditions

    Liver, kidney, and thyroid problems, pelvic inflammatory disease, leukemia, and certain cancers (uterine or cervical) are linked with heavy bleeding. Obesity and approaching menopause are risk factors.

    IUDs and Contraceptive Devices

    Hormone‑free intrauterine devices may cause heavier periods. Forgotten IUDs or implants can cause abnormal bleeding.

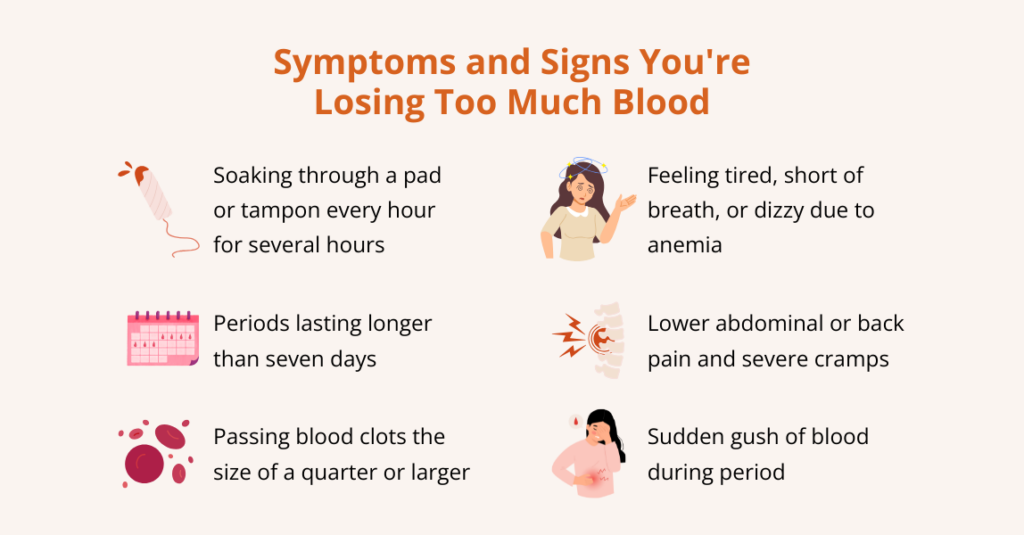
    Symptoms and Signs You’re Losing Too Much Blood

    Heavy menstrual bleeding can interfere with daily life and cause anemia. Warning signs include:

    • Soaking through a pad or tampon every hour for several hours, needing double protection, or changing pads at night.
    • Periods lasting longer than seven days. Some people report a period lasting two weeks or more.
    • Passing blood clots the size of a quarter or larger. Clots suggest that blood is pooling and clotting in the uterus.
    • Feeling tired, short of breath, or dizzy due to anemia. Iron deficiency can cause fatigue and palpitations.
    • Lower abdominal or back pain and severe cramps.
    • Sudden gush of blood during period that drenches clothes or bedding; this can be frightening and may suggest fibroids or endometrial polyps.

    If you bleed through two or more pads or tampons each hour for two or three hours, you should seek immediate medical care.

    Diagnosis: How Doctors Evaluate Heavy Menstrual Bleeding

    Doctors evaluate heavy period bleeding using a step-by-step approach to understand symptoms and identify the underlying cause.

    This process typically includes a detailed medical history, a physical and pelvic examination, and, when indicated, diagnostic tests.

    Patient History & Physical Exam

    The evaluation begins with a close review of the patient’s symptoms and the impact of heavy bleeding on daily life. Key areas include:

    Menstrual History

    The provider will ask about the age of the first period, cycle length and regularity, how long bleeding lasts, and how heavy the flow feels. Patients may be asked to keep a period diary, or track pad, or a tampon use to help estimate blood loss.

    Symptom Review

    Doctors look for clear signs of HMB, such as soaking through pads or tampons every hour for several hours, passing large blood clots (quarter-sized or larger), needing to change menstrual products during the night, or symptoms of anemia such as fatigue or shortness of breath.

    Medical and Family History

    The provider will review current health conditions (such as thyroid or liver problems), medications (including blood thinners), and any personal or family history of bleeding disorders or gynecologic cancers.

    Physical Examination

    This usually includes a general exam to check for signs of anemia and a pelvic exam to look for structural issues like fibroids or polyps, as well as signs of infection or other abnormalities.

    Diagnostic Tests

    A pelvic ultrasound is the most common test used by healthcare providers to evaluate menorrhagia.

    Based on the initial assessment, doctors may order one or more tests. Common diagnostic tests may include:

    • Blood tests to check for anemia, clotting problems, or thyroid disorders
    • A transvaginal ultrasound is used to closely examine the organs and tissues in the pelvis
    • Magnetic resonance imaging (MRI) is used if an ultrasound does not provide enough detail about the uterus
    • Pap smear to examine cervical cells for abnormal changes that could suggest cancer
    • Cervical culture to test for infection
    • Endometrial biopsy to analyze uterine tissue for cancer or other abnormalities

    Additional procedures that may help identify the cause include:

    • Sonohysterogram (saline-infusion sonography): A test in which saline is placed in the uterus to give a clearer view of the uterine lining and detect abnormalities.
    • Hysteroscopy: A procedure that allows the provider to look directly inside the vagina, cervix, and uterus to identify polyps, fibroids, or other abnormal tissue. In some cases, growths causing heavy bleeding can be removed during this procedure.

    Treatments for Heavy Menstrual Bleeding

    Treatment depends on the cause, severity, age, overall health, fertility goals, and personal preferences. Options range from lifestyle adjustments and supplements to medication and surgery.

    In some cases, menorrhagia may improve on its own without treatment. This is more likely when heavy bleeding is caused by mild hormonal changes or factors such as being overweight. For some individuals, menstrual bleeding may become lighter after achieving a healthier weight.

    It’s important to discuss your symptoms, overall health, and treatment goals with your healthcare provider.

    Home Remedies and Lifestyle Changes

    Some people seek ways to stop menstrual bleeding immediately or ask how to slow down period flow. While there is no “quick fix,” you may try these supportive measures:

    1. Stay Hydrated and Rest: Drink extra water to maintain blood volume and rest when needed.
    2. Cold Compress: Placing a cold pack on the lower abdomen may constrict blood vessels and temporarily reduce bleeding.
    3. Elevate Legs: Raising the legs while lying down can ease blood flow back to the heart.
    4. Avoid Aspirin: Choose ibuprofen or naproxen instead (if safe for you) because aspirin can increase bleeding.
    5. Discuss TENS (transcutaneous electrical nerve stimulation: Some find relief from cramps with TENS units.

    If heavy bleeding continues beyond seven days, see a healthcare provider.

    Medications to Treat Heavy Menstrual Bleeding

    Healthcare providers usually try medications first before recommending surgical treatment. Depending on the cause and severity of your symptoms, treatment options may include:

    • Iron supplements help restore low iron levels and treat or prevent anemia.
    • Nonsteroidal anti-inflammatory drugs (NSAIDs), such as ibuprofen or aspirin, can be used to reduce menstrual cramps and help lessen blood loss.
    • Birth control methods (including pills, patches, vaginal rings, and hormonal IUDs) are used to regulate menstrual cycles and reduce heavy bleeding.
    • Hormone replacement therapy (HRT) to balance estrogen and progesterone levels and reduce heavy flow; this option is often used during perimenopause and should be discussed carefully due to potential risks.
    • Gonadotropin-releasing hormone (GnRH) agonists or antagonists are used to reduce or stop menstrual bleeding temporarily.
    • Desmopressin nasal spray (Stimate®) to control bleeding in people with von Willebrand disease by improving blood clotting.
    • Antifibrinolytic medications, such as tranexamic acid, help prevent blood clots from breaking down and reduce excessive bleeding.

    Your healthcare provider can help determine which medication is most appropriate based on the cause of your heavy periods, overall health, and treatment goals.

    Minimally Invasive Procedures for Heavy Menstrual Bleeding

    When medications do not provide enough relief, healthcare providers may recommend procedures to control heavy menstrual bleeding.

    The choice depends on the cause of bleeding, symptom severity, and whether a future pregnancy is desired.

    Hysteroscopy

    This procedure allows the provider to look directly inside the uterus using a thin, lighted instrument. It is commonly used to identify and remove polyps or small fibroids located within the uterine cavity that may be causing heavy bleeding.

    Dilation and Curettage (D&C)

    During a D&C, the cervix is gently opened, and part of the uterine lining is removed. This can help reduce heavy bleeding and may also be used to diagnose underlying causes, such as abnormal tissue growth or complications related to pregnancy, including miscarriage.

    Myomectomy

    A myomectomy involves the surgical removal of uterine fibroids while preserving the uterus. This option is often recommended for people who wish to maintain fertility but need treatment for fibroids that cause heavy or painful periods.

    Uterine Fibroid Embolization (UFE)

    UFE is a minimally invasive procedure that blocks the blood supply to fibroids, causing them to shrink over time. As fibroids decrease in size, menstrual bleeding and related symptoms often improve.

    Endometrial Ablation or Resection

    These procedures destroy or remove all or part of the uterine lining using heat, lasers, freezing, or electrical energy. They can significantly reduce or stop menstrual bleeding. However, they are not recommended for people who plan to become pregnant, as the uterus may no longer support a healthy pregnancy.

    Hysterectomy

    A hysterectomy is the surgical removal of the uterus and is considered a permanent solution for heavy menstrual bleeding. It completely ends menstruation and fertility and is usually reserved for severe cases or when other treatments have not worked.

    Frequently Asked Questions (FAQs)

    How heavy is too heavy for a period?

    A period is generally considered “too heavy” when the amount of bleeding is more than what’s typical and starts to interfere with your life or health. In a typical menstrual cycle, most people lose about 2–3 tablespoons (30–40 mL) of blood over several days. Heavy menstrual bleeding (menorrhagia) is often defined as losing more than about 80 mL (roughly 5–6 tablespoons) of blood during a period, although exact measurement is hard to do in everyday life.

    Why is my period so heavy this month?

    Your period may be heavier than usual this month due to short-term hormone changes, stress, recent weight changes, or shifts in birth control. Other common causes include uterine conditions like fibroids or polyps, thyroid problems, perimenopause, certain medications (such as blood thinners), or pregnancy-related issues like an early miscarriage. Sometimes, a single heavy period occurs without a serious cause, but if the bleeding is very heavy, lasts more than 7 days, or affects your daily life, it’s important to consult a healthcare provider.

    Why am I bleeding so much on my period?

    Excessive bleeding (menorrhagia) can result from hormone imbalances, uterine growths, pregnancy issues, bleeding disorders, or medications. Only a healthcare provider can determine the exact cause through history and testing.

    When to go to the emergency for heavy menstrual bleeding?

    Go to the emergency room for heavy menstrual bleeding if you soak two or more pads or tampons per hour for several hours, pass large clots continuously, feel faint, or have trouble breathing. Heavy bleeding with severe pain or suspected pregnancy complications also warrants urgent medical attention.

    How to stop menstrual bleeding after 7 days?

    To stop menstrual bleeding that lasts more than 7 days, medical treatments like hormonal birth control (pills, IUD, or implant), NSAIDs, or tranexamic acid are most effective. Lifestyle measures, managing stress, staying hydrated, eating a balanced diet, and gentle exercise, may also help. However, prolonged bleeding should always be evaluated by a doctor to check for underlying health issues.

    How to stop heavy menstrual bleeding with clots?

    To stop heavy menstrual bleeding with clots, medical treatments are usually the most effective. Options include hormonal therapy such as birth control pills, IUDs, or high-dose progesterone, and tranexamic acid, which helps stabilize blood clots. NSAIDs like ibuprofen can reduce bleeding and relieve cramps. Lifestyle measures,  such as staying hydrated, managing stress, engaging in gentle exercise, and using appropriate menstrual products, can also help. However, if bleeding soaks a pad or tampon every hour, passes very large clots, lasts more than 7 days, or causes dizziness, fainting, or rapid heartbeat, it’s important to seek medical care immediately to rule out serious underlying issues and receive urgent treatment.

    Conclusion

    Heavy menstrual bleeding, or menorrhagia, is more than just an inconvenient period; it’s your body’s way of signaling that something may need attention.

    Causes can range from hormonal changes, fibroids or polyps, thyroid issues, pregnancy-related complications, to certain bleeding disorders.

    It’s important to recognize the warning signs: soaking through pads or tampons every hour, bleeding for more than seven days, passing large clots, or feeling unusually tired or weak.

    These symptoms are not something you have to just “live with.” A careful medical evaluation can help pinpoint the cause and guide the best treatment for you.

    Treatment options vary depending on your needs and may include lifestyle changes, iron supplements, NSAIDs, hormonal therapies, minimally invasive procedures, or, in rare cases, surgery.

    Most importantly, caring for yourself means seeking help without hesitation; you deserve to live your life fully without being held back by heavy periods.

  • Knee Pain: Its Causes, Diagnosis, Treatment, & Prevention

    Knee Pain: Its Causes, Diagnosis, Treatment, & Prevention

    Knee pain can quietly creep into your life or arrive in a single sudden moment, the twinge that stops you on the stairs, the ache that makes you skip a walk with a friend, or the sharp pain after a fall.

    Essentially, it is discomfort experienced in or around the knee, the largest joint in the body that bears your weight and allows movement such as bending, walking, and climbing.

    No matter how it appears, it’s more than a physical problem: it can frustrate your daily routine, steal small joys, and leave you worried about what’s next.

    This discomfort often arises from injuries, overuse, inflammation, arthritis, or other underlying conditions, and it can range from mild soreness to severe, debilitating pain.

    Fortunately, there are several ways to manage knee pain, depending on its cause.

    For example, home remedies such as rest, ice, and over-the-counter pain relief can help in the short term, while physical therapy and exercises strengthen the joint for longer-term improvement.

    Additionally, non-surgical treatments such as injections or minimally invasive procedures provide targeted relief, and in some cases, surgery may be necessary when other methods aren’t enough.

    In this post, we will explore what knee pain is, its causes, diagnosis, and treatment options, so you can understand your condition and take the right steps toward relief.

    What is Knee Pain?

    what is a knee pain

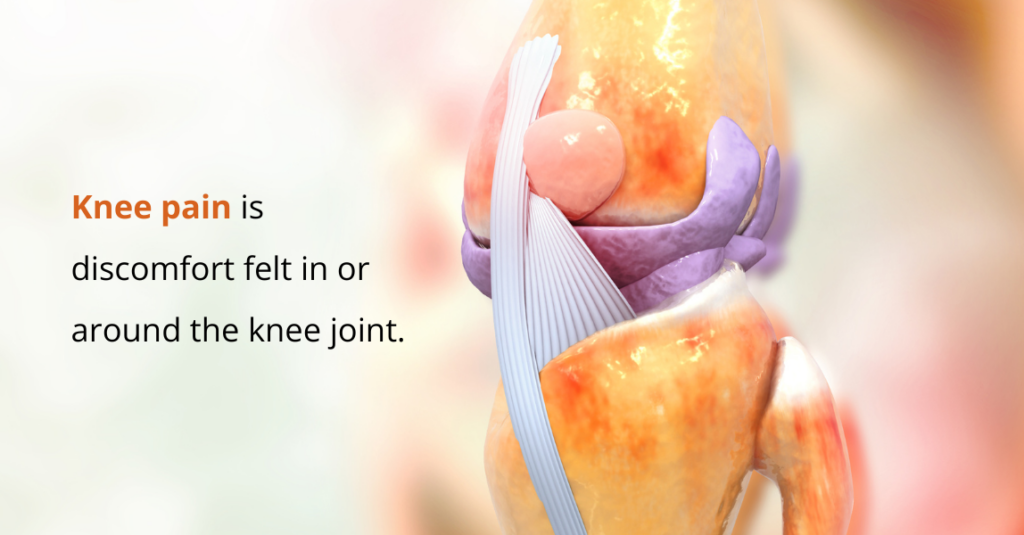
    Knee pain is discomfort felt in or around the knee joint, the largest joint in the body. Where you feel the pain can often give clues about what’s causing it.

    Your knee is a joint, the place where two bones meet. It connects your thigh bone (femur) to your lower leg bone (shin or tibia). This joint plays a major role in movement, balance, and weight support.

    The knee is the largest joint in the body and absorbs a lot of stress when you walk, run, bend, or climb stairs. Because of this, it’s one of the most commonly injured joints. Knee pain can be short-term and temporary, or it can become a long-term (chronic) condition.

    Some people notice pain when moving, bending, or putting weight on the knee, while others feel relief when resting. Pain may also vary throughout the day, often worse in the morning, at night, or after physical activity.

    What are the Causes of Knee Pain?

    what are the causes of a knee pain

    Knee pain can come from many different problems. Sometimes it’s due to an injury from a fall, twist, or sports activity. At other times, it develops over time due to wear and tear, inflammation, or other medical conditions.

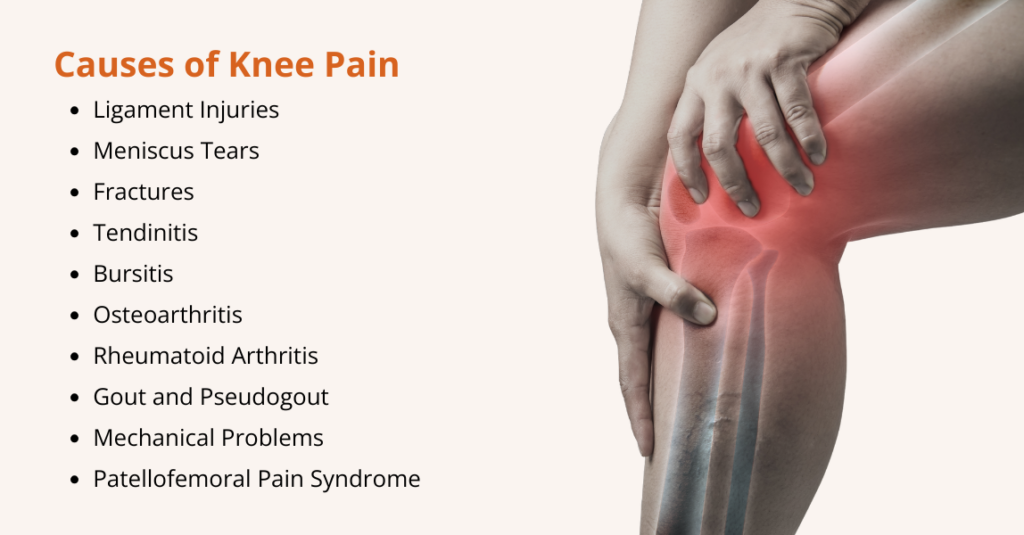
    Here are the main causes of knee pain:

    • Ligament Injuries

    Tears or sprains of ligaments such as the ACL, PCL, MCL, or LCL often occur with sudden twists, stops, or impacts. They can cause pain, swelling, and instability.

    • Meniscus Tears

    The meniscus is cartilage that cushions the knee. A tear often from twisting the knee while bearing weight can lead to pain, stiffness, and difficulty moving.

    • Fractures

    A fracture of the kneecap or nearby bones can result from falls, collisions, or other trauma. This causes sharp pain and usually needs prompt care.

    • Tendinitis

    Overuse of the tendons around the knee (especially the patellar tendon) can cause inflammation. This common condition, known as “jumper’s knee,” causes pain during activity.

    • Bursitis

    The bursae are small fluid-filled sacs that cushion the knee. When they become irritated or inflamed, they cause pain and swelling, especially with pressure or movement.

    • Osteoarthritis

    This “wear-and-tear” arthritis happens when the protective cartilage of the knee wears down over time, leading to pain, stiffness, and swelling.

    • Rheumatoid Arthritis

    An autoimmune condition in which the body’s immune system attacks the joints, causing inflammation, pain, and potentially long-term damage.

    • Gout and Pseudogout

    These are caused by tiny crystals forming in the joint, which can trigger sudden and severe pain, redness, and swelling.

    • Mechanical Problems

    Issues such as a dislocated kneecap, a loose piece of bone/cartilage floating in the joint, or irritation of the iliotibial (IT) band can all trigger pain by affecting knee mechanics.

    • Patellofemoral Pain Syndrome

    Pain around or under the kneecap, common among athletes and active individuals, often results from misalignment, overuse, or muscle imbalance.

    How to Diagnose Knee Pain?

    how to diagnose a knee pain

    To diagnose knee pain, health care providers combine your medical history, a physical exam, and, if needed, special tests or imaging to see inside the joint.

    Medical History

    Your doctor or clinician will ask questions about:

    • When the pain started and how it began (suddenly or gradually)
    • What movements make it worse or better
    • Any recent injuries or activities that could have caused strain
    • Other symptoms like swelling, stiffness, or instability

    Physical Exam

    During the exam, your provider will:

    • Look at your knee for swelling, bruising, warmth, or tenderness
    • Check how far you can bend and straighten the knee
    • Move your knee in different directions to test stability
    • Feel for pain or weakness in specific areas

    These tests help identify which structures (ligaments, tendons, cartilage, bones) might be involved.

    Imaging Tests

    Imaging helps doctors see inside the knee when the physical exam isn’t enough or the pain is severe:

    • X-ray: First and most common test. It shows bone fractures, joint space narrowing (arthritis), and bone alignment problems.
    • MRI (Magnetic Resonance Imaging): It provides detailed images of soft tissues, including ligaments, tendons, cartilage, and menisci. It’s very useful when a tear or soft tissue injury is suspected.
    • CT Scan: Provides detailed bone images and may be used when X-rays are unclear or when fractures are difficult to visualize.
    • Ultrasound: Uses sound waves to view soft tissues and see fluid or tendon injuries in real time.
    • Bone Scan or Arthroscopy: Sometimes used in special cases to find bone activity or to directly look inside the joint with a camera.

    Lab Tests and Joint Fluid Analysis

    If the doctor suspects infection, inflammation, or arthritis, they may order:

    • Blood tests (e.g., inflammation markers or autoimmune markers)
    • Joint aspiration: Removing a small amount of fluid from the knee with a needle to check for infection, crystals (like in gout), or inflammation.

    Your clinician will combine information from your history, exam, and test results to make a diagnosis.

    What are the Treatments for Knee Pain Relief?

    how to treat a knee pain

    Knee pain treatment usually involves a combination of therapies and, when necessary, surgery. The best approach depends on the cause of the pain, its severity, and the patient’s individual needs and goals.

    Rest, Ice, Compression & Elevation (RICE)

    These simple steps help reduce pain, swelling, and stiffness—especially right after an injury.

    • Rest: Take a break from activities that hurt.
    • Ice: Apply a cold pack wrapped in a towel to reduce swelling and numb pain.
    • Compression: Wrap the knee with a bandage to limit fluid buildup.
    • Elevation: Raise the leg on pillows to facilitate drainage away from the knee.

    Over-the-Counter Pain Relief

    Over-the-counter pain medications can help manage knee pain. NSAIDs (like ibuprofen or naproxen) reduce pain and, at higher doses, inflammation, but should be used with caution if you have stomach ulcers, bleeding disorders, or certain kidney conditions.

    Moreover, topical treatments such as gels or creams containing menthol or capsaicin can provide local pain relief. For more severe pain, doctors may recommend prescription-strength medications.

    Physical Therapy & Exercise

    A physical therapist can show you exercises to:

    • Strengthen the muscles around your knee
    • Improve flexibility and balance
    • Reduce stress on the joint

    Regular physical activity, such as walking, swimming, cycling, tai chi, or yoga, can also help with long‑term knee pain and improve mobility.

    Braces & Supportive Devices

    Knee braces, sleeves, or shoe inserts can:

    • Help stabilize the knee joint
    • Reduce strain during activities
    • Improve alignment and comfort

    These are often used alongside exercise or therapy.

    Non-Surgical Options

    There are non-surgical options for managing knee pain that provide relief without surgery.

    • Genicular Artery Embolization (GAE): GAE is a minimally invasive procedure performed by an interventional radiologist. Tiny particles are used to block blood flow to inflamed areas around the knee, thereby reducing chronic pain, particularly in osteoarthritis.
    • Intra-Articular Injections: Intra-articular injections deliver medications, such as corticosteroids, hyaluronic acid, or platelet-rich plasma, directly into the knee joint. These injections help reduce inflammation, improve joint lubrication, and relieve pain.

    Surgery (When Needed)

    If conservative treatments don’t help and the pain is disabling, surgery may be considered:

    • Arthroscopy: Small repairs inside the knee
    • Partial or total knee replacement: Replaces damaged joint surfaces
    • Osteotomy: Realigns bones to take pressure off worn areas

    These options are usually for severe injuries, advanced arthritis, or cases that limit daily activities.

    How to Prevent Knee Pain?

    Keeping your knees healthy is mostly about smart movement, good habits, and a few common-sense safety steps. Try these practical tips to lower your risk of injury and long-term pain:

    • Warm up and cool down: Spend 5–10 minutes warming up (light walking, gentle movement) before exercise and cool down with slow walking and stretching afterward to protect muscles and joints.
    • Build strength and flexibility: Perform regular exercises targeting the quadriceps, hamstrings, hips, and core, and incorporate gentle stretching or mobility exercises.
    • Increase activity gradually: Raise intensity, distance, or weight slowly, and don’t jump into a harder routine overnight.
    • Choose low-impact options: Swap high-impact activities (sprinting, repetitive jumping) for cycling, swimming, or elliptical workouts when possible to reduce joint stress.
    • Use proper technique and gear: Learn correct form for sports and lifting. Wear supportive shoes and use protective equipment (e.g., knee pads, braces) as appropriate.
    • Listen to your body: If your knee hurts during or after activity, stop, rest, and consult a professional before continuing.
    • Manage weight and overall health: Keeping a healthy weight reduces pressure on the knees. Control chronic conditions (like diabetes or arthritis) that can affect joint health.
    • Make your home safer: Remove tripping hazards, use stable step stools (not chairs), install handrails where needed, and use a cane or walker if you’re at risk of falling.

    Small, consistent choices add up, protecting your knees today helps keep you active and pain-free tomorrow.

    Frequently Asked Questions (FAQs)

    Why do I have knee pain?

    Knee pain can result from many causes, ranging from injuries to long-term joint conditions. Common causes include:

    • Injuries: Sprains, ligament tears (like ACL or MCL), meniscus tears, or fractures can cause sudden pain, swelling, or instability.
    • Arthritis: Osteoarthritis or rheumatoid arthritis gradually wears down the joint, leading to chronic pain, stiffness, and swelling.
    • Overuse: Repetitive activities such as running, jumping, or kneeling can strain the muscles, tendons, and ligaments around the knee.
    • Inflammation: Conditions such as bursitis or tendinitis can irritate the tissues surrounding the knee.
    • Mechanical issues: Problems such as a dislocated kneecap, loose cartilage, or alignment problems can cause pain during movement.

    Your knee may also be affected by a combination of these factors. Understanding the cause is important for choosing the right treatment, from rest and physical therapy to medications, injections, or minimally invasive procedures.

    What is the fastest way to relieve knee pain?

    While long-term relief depends on treating the underlying cause, you can ease knee pain quickly using these methods:

    • Rest the Knee: Avoid activities that worsen pain or put weight on the joint. Short-term rest reduces strain.
    • Ice Therapy: Apply a cold pack for 15–20 minutes several times a day to reduce pain and swelling.
    • Compression: Use an elastic bandage or knee sleeve to support the joint and limit swelling.
    • Elevation: Raise your leg on pillows so the knee is above heart level to help fluid drain away.
    • Over-the-Counter Pain Relievers: NSAIDs (such as ibuprofen or naproxen) quickly reduce pain and inflammation. Acetaminophen may be beneficial if inflammation is not the primary issue.
    • Topical Pain Creams: Menthol or capsaicin gels applied to the knee can provide fast local relief.
    • Gentle Movement: Light stretches or walking (if tolerable) can prevent stiffness and maintain circulation.

    What’s the best thing for knee pain?

    The best approach for knee pain combines exercise and physical therapy to strengthen the joint, pain relief with ice or medications, and, if needed, injections or minimally invasive treatments for persistent pain, with surgery as a last resort.

    What can I take for knee pain?

    For knee pain, you can take over-the-counter medications such as NSAIDs (e.g., ibuprofen, naproxen) to reduce pain and inflammation, or acetaminophen for pain relief without anti-inflammatory effects. Topical creams or gels (e.g., menthol or capsaicin) can provide local relief. For persistent pain, doctors may recommend prescription medications or intra-articular injections.

    When should I see a doctor for knee pain?

    Most mild knee pain can improve with rest, home care, and over-the-counter treatments. However, you should consult a healthcare professional if you experience any of the following:

    • Severe or sudden pain that doesn’t improve with rest
    • Swelling, redness, or warmth around the knee
    • Inability to bear weight or move the knee normally
    • Deformity or popping/clicking sounds after an injury
    • Pain that persists for several weeks despite home treatment
    • Fever or signs of infection in the knee
    • Recurring or worsening pain that affects daily activities

    Early evaluation helps prevent complications, ensures accurate diagnosis, and allows for timely treatment.

    Conclusion

    Knee pain can be more than just a physical discomfort. It can disrupt daily life, limit activities you enjoy, and leave you feeling frustrated or worried about the future.

    Understanding why your knee hurts is the first step toward finding relief. Whether it stems from an injury, overuse, arthritis, or inflammation, identifying the cause helps guide the right treatment.

    Simple measures such as rest, ice, and over-the-counter pain relievers can ease discomfort, while physical therapy and targeted exercises can strengthen the joint and improve mobility.

    Non-surgical options, such as injections or minimally invasive procedures, offer relief for persistent pain, and surgery is reserved for cases where other treatments aren’t enough.

    Remember, knee pain doesn’t have to define your life.

    Seeking timely advice, understanding your options, and following a personalized treatment plan can help you regain comfort, restore movement, and return to the activities you love.

    Taking the first step toward care is the start of reclaiming your freedom.

  • Urinary Retention, Causes, Symptoms, Diagnoses, & Treatments

    Urinary Retention, Causes, Symptoms, Diagnoses, & Treatments

    Urinary retention is a condition where the bladder does not empty properly.

    For many people, it starts as a heavy or tight feeling in the lower abdomen. You may feel a strong urge to urinate but struggle to start, strain to pass urine, or release only a small amount even though your bladder still feels full.

    This can be uncomfortable, frustrating, and sometimes painful.

    In some cases, urinary retention happens suddenly and causes severe pain and pressure. In others, it develops slowly over time.

    Because these symptoms can build up gradually, they are sometimes ignored until the discomfort becomes hard to manage.

    Urinary retention can affect both men and women and may be linked to blockages, nerve problems, medications, infections, or recent surgery.

    This guide explains what urinary retention is, its causes, signs, and symptoms, how it is diagnosed, and the treatment options available, so you can better understand what is happening and what steps to take next.

    What is Urinary Retention?

    what is urinary retention

    Urinary retention is a condition where your bladder does not empty fully, or cannot empty at all, when you urinate (pee). This means urine stays trapped inside the bladder instead of flowing out normally.

    Your bladder works like a storage tank. Your kidneys filter waste from your blood and turn it into urine. That urine travels to your bladder, where it is stored until you’re ready to urinate.

    When you pee, the bladder muscles squeeze, and urine flows out through the urethra.

    With urinary retention, this process does not work properly. The bladder may not squeeze properly, the urethra may be blocked, or the nerves may not send the right signals. As a result, urine stays in the bladder, causing pressure, discomfort, and other urinary problems.

    What Causes Urinary Retention?

    Urinary retention can happen for several different reasons. Common causes can include:

    • A blockage in the urine flow
    • Medications that affect the nervous system
    • Nerve problems that stop the brain and the urinary system from communicating
    • Infections or inflammations can block or slow the flow
    • Surgery or anesthesia can cause retention

    While these causes apply to both men and women, the specific reasons for urinary retention often differ by sex due to anatomical differences and common health conditions.

    What are the Causes of Urinary Retention in Females?

    what are the causes of urinary retention in females

    The most common and female-specific causes include:

    Pelvic Organ Prolapse (POP)

    Sometimes the bladder, uterus, or other pelvic organs sag or drop down. When the bladder bulges into the vagina (a cystocele), it can kink the bladder outlet or press on the urethra, making it hard to empty fully.

    Childbirth & Pregnancy

    Pregnancy and vaginal delivery can stretch or injure the pelvic muscles and nerves that help you pee. A very full uterus or an unusual uterus position (like a retroverted uterus) can press on the bladder.

    Epidural anesthesia during labor can also make the bladder less able to squeeze for a short time.

    Fowler’s Syndrome

    A less common problem in younger women is where the ring of muscle around the urethra (the sphincter) doesn’t relax properly. That tightness obstructs urine flow even when the bladder is full.

    Pelvic Surgery or Trauma

    Operations on the pelvis (for example, for urine incontinence or hysterectomy) or injuries can damage nerves or change the shape of pelvic organs. That can weaken bladder control or cause a physical condition that impedes the flow of urine.

    Menopause

    Lower hormone levels after menopause result in thinner, less elastic pelvic tissues. The urethral opening can narrow, and weak tissues can alter the position of the bladder and urethra, which may lead to difficulty emptying.

    Uterine Fibroids and Pelvic Tumors

    Noncancerous growths (fibroids) or other pelvic masses can press on the bladder or urethra. That pressure can partially obstruct urine flow or make it difficult to fully empty the bladder.

    What are the Causes of Urinary Retention in Males?

    what are the causes of urinary retention in males

    The most common and male-specific causes include:

    Benign Prostatic Hyperplasia (BPH)

    As men get older, the prostate gland often becomes enlarged. The prostate sits just below the bladder and surrounds the urethra (the tube that carries urine out of the body). When it enlarges, it can squeeze the urethra, slowing or blocking urine flow.

    Prostatitis

    Prostatitis is inflammation or infection of the prostate. It can cause the prostate to swell suddenly, narrowing the urethra.

    Prostate Cancer

    Prostate cancer can also press on the urethra and block urine flow. Unlike infections, this usually develops slowly over time.

    Urethral Stricture

    A urethral stricture occurs when scar tissue narrows the urethra. This scar tissue can form after injury, surgery, catheterization, or infection (e.g., sexually transmitted infections), restricting urinary flow.

    Phimosis and Paraphimosis

    These conditions affect uncircumcised men.

    • Phimosis happens when the foreskin cannot be pulled back over the tip of the penis, which can trap urine and cause swelling.
    • Paraphimosis occurs when the foreskin is pulled back but cannot return to its normal position, causing painful swelling that can block urine flow.

    Penile Trauma (Injury)

    Injury to the penis, such as from an accident, fall, or sports injury, can cause swelling, bleeding, or damage to the urethra. This swelling or damage can block urine flow and lead to sudden urinary retention.

    What are the Signs and Symptoms of Urinary Retention?

    The symptoms of urinary retention can be different depending on whether it is acute (sudden) or chronic (long-term).

    Some people, especially those with nerve damage, may not feel pain even when the bladder is not emptying properly.

    Acute (Sudden)

    People with acute urinary retention (AUR) may experience:

    • Sudden inability to urinate despite a strong urge
    • Severe pressure, pain, or discomfort in the lower abdomen
    • Swelling or bloating in the lower belly
    • Lower back pain

    Chronic (Long-Term)

    Chronic urinary retention (CUR) typically develops gradually and may not cause severe pain initially. People with chronic urinary retention may experience:

    • Trouble starting urine flow
    • A weak or slow urine stream
    • A urine stream that stops and starts
    • A strong urge to urinate, but passing only a small amount
    • Feeling the need to urinate again right after going
    • Frequent trips to the bathroom, including at night
    • Mild, ongoing discomfort in the lower abdomen or urinary tract
    • Leakage of urine during sleep or at rest due to bladder overflow

    ​How is Urinary Retention Diagnosed?

    ​how is urinary retention diagnosed

    Healthcare professionals diagnose urinary retention by reviewing your medical history, performing a physical exam, and measuring how much urine remains in your bladder after you urinate (called a post-void residual).

    Additional lab tests and imaging studies may be ordered to find the exact cause.

    Medical History

    Your health care professional will ask detailed questions about your health and symptoms, including:

    • Urinary symptoms (also called lower urinary tract symptoms)
    • Current and past medical conditions, surgeries, or catheter use
    • Prostate problems (in men)
    • Pregnancy and childbirth history (in women)
    • Over-the-counter and prescription medications
    • Eating and drinking habits
    • Bowel habits

    This information helps identify possible triggers or underlying causes.

    Physical Exam

    A physical exam is done to look for signs of bladder or nerve problems. This may include:

    • Checking your lower abdomen for a full or swollen bladder
    • A rectal exam to examine the prostate (in men)
    • A pelvic exam (in women)
    • A basic neurological exam to assess nerve function

    Post-Void Residual (PVR) Urine Measurement

    A post-void residual test measures how much urine remains in your bladder after you urinate. The leftover urine is called the post-void residual.

    This test is done using:

    • A small catheter is placed briefly into the bladder, or
    • A bladder ultrasound scan
    • A high amount of leftover urine suggests urinary retention.

    Lab Tests

    Your health care professional may order lab tests to look for conditions linked to urinary retention, such as:

    • Urinalysis: Checks for urinary tract infection (UTI), kidney problems, or diabetes
    • Blood tests: Check kidney function and chemical imbalances in the body

    You may be asked to provide a urine sample for testing.

    Imaging Tests

    Imaging tests help identify structural problems or blockages in the urinary tract. These may include:

    • Ultrasound: Uses sound waves to view the bladder, kidneys, and urinary tract
    • Voiding cystourethrogram (VCUG): Uses X-rays to show how urine flows through the bladder and urethra
    • MRI (magnetic resonance imaging): Creates detailed images of the urinary tract and spine
    • CT scan: Provides detailed cross-sectional images of the urinary system

    Urodynamic Testing

    Urodynamic tests check how well the bladder, urethra, and sphincter muscles store and release urine. These tests may include:

    • Uroflowmetry: Measures how much urine you pass and how fast
    • Pressure-flow studies: Measure bladder pressure and urine flow during urination
    • Video urodynamics: Uses images or video to show bladder filling and emptying
    • Cystometry: Measures bladder capacity and pressure as it fills
    • Electromyography: Tests how well nerves and muscles around the bladder work together

    Cystoscopy

    Cystoscopy is a procedure in which a thin, flexible tube with a camera (a cystoscope) is inserted into the urethra to visualize the urethra and bladder. This helps doctors check for:

    • Blockages or narrowing
    • Inflammation or infection
    • Tumors or cancer
    • Structural abnormalities

    Urinary Retention Treatment Options

    urinary retention treatment options

    There are several treatment options for urinary retention, including the following:

    Catheterization

    Acute urinary retention is a medical emergency. If you suddenly can’t pee at all, a doctor will quickly drain your bladder. This is usually performed by inserting a thin tube (a catheter) through the urethra into the bladder to allow urine to flow out.

    Draining the bladder relieves pain and prevents damage to your bladder or kidneys. Once the bladder is empty, doctors will treat the cause (for example, an enlarged prostate, a blood clot, or an infection).

    In some cases of long-term (chronic) retention, people learn to use a catheter at home to empty their bladder regularly.

    Home Remedies

    While medical treatment is essential for urinary retention, some gentle at-home tricks can help encourage urination. These are not cures, but they may make it easier to go until you can see a doctor:

    • Warm water and sound: Sit on the toilet and run warm water from the tap. The sound and feel of warm water can sometimes trigger bladder emptying.
    • Warm bath or perineal rinse: A warm sitz bath or rinsing the genital area with warm water can relax pelvic muscles.
    • Body position and relaxation: Lean slightly forward while sitting on the toilet (for women, putting feet on a small stool) and take deep breaths.
    • Walking and gentle movement: Sometimes a short walk or light activity can help stimulate bladder function or relieve constipation, which in turn can facilitate urination.
    • Peppermint oil: Some individuals report that the scent of peppermint oil may facilitate urination.
    • Herbal teas: Teas made from herbs such as dandelion or stinging nettle are sometimes used to relieve bladder symptoms.

    If you still cannot urinate or have severe pain, seek medical help right away. Home tips are intended only for mild cases or for use while waiting for care.

    Lifestyle & Behavioral Changes

    Certain habits and exercises can support treatment and ease symptoms over time. These changes are especially useful for chronic retention or after initial treatment:

    • Bladder training: Go to the toilet at regular times, even if you don’t feel a strong urge. For example, try urinating every 2–4 hours.
    • Double voiding: After you urinate, wait a minute and then try again. This “double peeing” helps make sure your bladder is as empty as possible.
    • Relax on the toilet: Take a moment to relax while seated fully. Breathe deeply and give yourself time. For women, sitting with the knees apart (or even slightly squatting) allows the pelvic muscles to relax more effectively.
    • Fluid management: Drink adequate water during the day, but limit fluids before bedtime to avoid nocturnal retention.
    • Avoid bladder irritants: Cut down on caffeine (coffee, tea, cola), alcohol, and carbonated drinks, as these can irritate the bladder and make retention worse.
    • Go when you need to: Don’t “hold it” when you feel the urge. Responding promptly to the urge to urinate helps prevent bladder overstretching.
    • Manage constipation: Straining during defecation can worsen retention by compressing the bladder or pelvic nerves.
    • Weight and posture: Maintaining a healthy weight and good posture can reduce pressure on pelvic organs. Lifting properly (bending the knees, not the back) can also help prevent problems.

    Making these changes takes time, but they are low-risk ways to help your bladder. Always discuss lifestyle plans with your doctor or nurse.

    Medication

    Your health care provider may prescribe medicines to treat the underlying cause of urinary retention. The type of medication depends on what is preventing your bladder from emptying properly.

    • Enlarged prostate (in men): Medicines such as alpha-blockers help relax the muscles around the prostate and bladder neck, making it easier for urine to flow. 5-alpha reductase inhibitors work by slowly shrinking the prostate, which can reduce blockage over time.
    • Infections: If an infection is causing swelling or blockage, antibiotics are used to clear the infection and relieve urinary retention.

    Medical Procedures

    If medicines and behavior changes aren’t enough, doctors have many procedures and therapies to fix the cause of retention:

    • Cystoscopy and stone removal: A cystoscope is a thin, lighted tube passed into the bladder. It allows the physician to see inside and remove any stones or growths obstructing urine flow.
    • Urethral dilation: If a urethral stricture (scar tissue narrowing the urethra) is the problem, the doctor can stretch or widen the urethra during an office visit.
    • Vaginal pessary (women): In women with pelvic organ prolapse, a pessary is a removable ring placed inside the vagina to hold the bladder up.
    • Pelvic floor therapy: A specialized pelvic-floor therapist can use biofeedback, electrical stimulation, or manual techniques to improve pelvic muscle function.

    Frequently Asked Questions (FAQs)

    Can UTI cause urinary retention?

    Yes, a urinary tract infection (UTI) can cause urinary retention. When the bladder or urethra becomes inflamed or swollen due to infection, it can block or slow the flow of urine. In some cases, the bladder muscles may also become weak or unable to contract properly, making it difficult to empty the bladder completely. Urinary retention and UTIs can also make each other worse: urine left in the bladder provides a place for bacterial growth, increasing the risk of infection. If you experience difficulty urinating along with symptoms of a UTI, such as burning, urgency, or lower abdominal discomfort, it’s essential to seek medical care promptly.

    Can urinary retention be cured?

    Yes, urinary retention can often be cured or well-managed. Treatment usually involves draining the bladder and addressing the underlying cause, which may include an enlarged prostate, infections, or nerve problems. Depending on the cause, doctors may use catheters, medications, pelvic floor therapy, or surgery to restore normal urination, relieve discomfort, and improve bladder function.

    Does constipation cause urinary retention?

    Yes, constipation can contribute to urinary retention. A full rectum can press on the bladder or urethra, making it hard to empty, and straining can weaken pelvic muscles or interfere with the nerves that control urination. This can lead to incomplete bladder emptying and increase the risk of urinary tract infections.

    Can you die from urinary retention?

    Yes, urinary retention can be life-threatening, but usually only if complications develop. When urine stays in the bladder for too long, it can lead to serious infections that may spread to the kidneys or bloodstream, causing sepsis, a dangerous body-wide reaction that can result in organ failure. It can also cause acute kidney damage if the blockage prevents urine from leaving the body.

    What can urinary retention lead to?

    Urinary retention can lead to several complications if it isn’t treated, including:

    • Urinary tract infections (UTIs): Residual urine allows bacteria to grow, increasing the risk of recurrent or severe infections.
    • Bladder damage: A chronically overfilled bladder can stretch and weaken, reducing its ability to contract and empty.
    • Overflow incontinence: The bladder may leak small amounts of urine when it becomes overly full.
    • Urine backup in the kidneys (hydronephrosis): A blockage can cause urine to flow backward into the kidneys, leading to swelling and damage.
    • Acute kidney injury/chronic kidney disease: Severe or prolonged obstruction can impair kidney function.
    • Sepsis (blood infection): A UTI that spreads can lead to life-threatening sepsis, particularly in older adults or immunocompromised individuals.
    • Stones and irritation: Stagnant urine can lead to bladder stones and ongoing irritation or inflammation.
    • Sexual dysfunction & reduced quality of life: Ongoing urinary problems can affect sexual function, sleep, mood, and daily activities.
    • Falls or injuries: Nighttime urgency or hurried bathroom trips increase the risk of falls, particularly among older adults.
    • When to get urgent care: inability to urinate at all, severe belly pain, fever, chills, confusion, vomiting, fainting, or decreased urine output. These can signal serious complications and need immediate medical attention.

    How long before urinary retention is dangerous?

    If urinary retention is acute (sudden), it becomes dangerous right away, and you should seek emergency care the moment you cannot urinate because immediate bladder drainage is needed to prevent pain and complications. Research shows that obstruction can cause acute kidney injury within hours to days, and the risk of lasting kidney damage rises noticeably after about 48–72 hours of ongoing blockage. Whereas chronic (long-term) retention is less often immediately life-threatening but can slowly cause bladder damage, infections, stones, and kidney problems over weeks to months if not treated.

    How long does post-operative urinary retention last?

    Postoperative urinary retention (POUR) usually improves on its own, with most patients regaining normal urination within a few days to a few weeks after surgery. In some cases, it can last 4–6 weeks, and rarely even longer, depending on the type of surgery, anesthesia used, and individual factors. Retention often resolves as the effects of anesthesia wear off and urinary tract swelling decreases. Still, prolonged cases may require additional interventions, such as catheterization, medications, or further evaluation by a healthcare provider.

    How to prevent urinary retention?

    You can often reduce the risk of urinary retention by addressing factors that compress the bladder, interfere with emptying, or disrupt nerve function. Here’s how:

    • Perform pelvic floor exercises (Kegels) or consult a pelvic floor therapist to maintain muscle function.
    • Avoid constipation by increasing fiber intake, maintaining adequate hydration, exercising, and using gentle laxatives or stool softeners if needed, as a full rectum can press on the bladder.
    • Drink regularly during the day but cut down before bedtime; avoid excess caffeine and alcohol that irritate the bladder.
    • Get UTIs or prostatitis checked and treated promptly so swelling does not block urine flow.
    • Review medicines with your clinician, as some drugs (antihistamines, strong painkillers, decongestants) can cause retention; your doctor may adjust them.
    • Manage prostate and pelvic conditions, follow up for BPH, prolapse, or fibroids, so mechanical blockages are identified and treated.
    • Sit properly, take your time, try “double voiding” (pee, wait a minute, try again), and don’t ignore urges.
    • After surgery, follow post-op care, as early walking, pain control, and close bladder checks reduce the risk of postoperative retention.
    • See your doctor for regular checks if you have diabetes, spinal problems, prior pelvic surgery, or recurrent urinary issues.

    If you start having trouble emptying your bladder, sudden inability to urinate, severe pain, fever, or worsening symptoms, seek medical help right away.

    Doctors who treat acute urinary retention

    Doctors who treat acute urinary retention (AUR) are mainly urologists, specialists in the urinary and reproductive systems, who manage immediate bladder drainage with a catheter and treat the underlying cause through medications or procedures. If you cannot see a urologist immediately, going to the emergency room is essential, where an emergency physician can provide urgent care and relieve the obstruction. Other healthcare professionals, such as nurse practitioners, physician assistants, and pelvic floor physical therapists, may also be involved in ongoing management and rehabilitation to prevent recurrence and improve bladder function.

    Conclusion

    Urinary retention can be uncomfortable, frustrating, and even frightening, especially when you feel a full bladder but cannot urinate.

    This condition is fairly common and can occur suddenly (acute) or develop over time (chronic), with causes ranging from infections, an enlarged prostate, nerve problems, pelvic organ prolapse, to certain medications.

    As a result, symptoms can vary widely, from difficulty starting urination and a weak urine stream to an inability to urinate, lower abdominal pain, or frequent urination.

    To determine the cause, diagnosis typically involves obtaining a detailed medical history, performing a physical examination, performing urinalysis, and, in some cases, using imaging or specialized bladder studies.

    Based on the findings, treatment depends on the severity and underlying cause of the retention. Available options include immediate catheterization, medications, nonsurgical therapies, lifestyle adjustments, and, when necessary, surgical intervention.

    It is important to remember that if you are experiencing urinary difficulties, you are not alone, and medical help is available to restore comfort, improve bladder function, and provide peace of mind.

  • Dr. Zagum Bhatti: Pioneering Minimally Invasive Care at Seamless Medical Centers

    Dr. Zagum Bhatti: Pioneering Minimally Invasive Care at Seamless Medical Centers

    If you’ve ever felt like just another number in a crowded waiting room, or wondered if your doctor was recommending a procedure based on what’s best for you or what’s best for the hospital’s bottom line, you’re not alone. These frustrations drove Dr. Zagum Bhatti to completely reimagine what patient care could look like.

    For Dr. Zagum Bhatti, a board-certified interventional radiologist and minimally invasive procedure specialist, the conviction that patients deserve better has been the guiding principle throughout his distinguished career. Frustrated by a healthcare system that often prioritizes the bottom line over individual well-being, Dr. Bhatti founded Seamless Medical Centers—a practice where he could revolutionize the entire patient experience, from start-to-finish.

    Educational Excellence: The Foundation of Expertise

    Dr. Bhatti’s journey to becoming one of Texas’s leading interventional radiologists began with rigorous medical training at some of the nation’s most prestigious institutions.

    He earned his medical degree from the Medical College of Wisconsin, consistently ranked among America’s top medical schools for clinical excellence and innovative research. Following medical school, Dr. Bhatti completed his Diagnostic Radiology Residency at Michigan State University College of Human Medicine in Grand Rapids, Michigan, from 2008 to 2013. His exceptional clinical skills and leadership abilities earned him the prestigious position of Chief Resident—an honor reserved for the most outstanding residents who demonstrate excellence in patient care, teaching ability, and leadership.

    Dr. Bhatti completed two fellowship programs to develop his specialized skills. His Fellowship in Neuroradiology at the Medical College of Wisconsin focused on imaging the brain, spine, and nervous system. He then completed a Fellowship in Vascular and Interventional Radiology at Rush University Medical Center in Chicago, where he trained in minimally invasive, image-guided procedures.

    With 17 years of medical experience, Dr. Bhatti has performed thousands of successful minimally invasive procedures. His extensive hands-on experience and proficiency in interventional radiology allow Dr. Bhatti to deliver effective, precise care for his patients.

    The Seamless Difference: Patient-Centered Philosophy

    Why Dr. Bhatti Founded His Own Practice

    Throughout his career, Dr. Bhatti witnessed a troubling pattern: patients being pushed toward more invasive, expensive procedures when minimally invasive alternatives could achieve equal or better outcomes with less risk and faster recovery. The healthcare system’s financial incentives often seemed misaligned with patient interests.

    This frustration drove him to found Seamless Medical Centers, where he could control every aspect of the patient experience and ensure that treatment decisions are based solely on what’s best for each individual patient.

    What Makes Seamless Medical Centers Different?

    Comprehensive, Unhurried Consultations: Unlike rushed appointments common in traditional healthcare settings, Dr. Bhatti and his team ensure patients fully understand their condition and all available treatment options. The philosophy at Seamless is that informed patients make better decisions about their health.

    Truly Minimally Invasive Care: Most procedures are performed via pinhole access point just 2-3 millimeters wide. Advanced image guidance allows Dr. Bhatti to treat only the affected areas while preserving healthy tissue. According to the Society of Interventional Radiology, minimally invasive procedures significantly reduce risks of infection, bleeding, and other complications compared to surgery. Patients are discharged the same day as their procedure and generally return to normal activities within just a few days.

    Transparent Decision Making: Dr. Bhatti recommends the best treatment option even if it’s not one his practice offers, provides transparent discussion of all risks and benefits, and respects patient preferences and values. Patients are true partners in their care—never pressured toward procedures they don’t need.

    Outstanding Patient Reviews

    The true measure of Dr. Bhatti’s approach to patient care comes from those he’s treated. Patients consistently share stories of transformative experiences—from walking pain-free after procedures they thought would require lengthy recoveries, to finally finding a physician who takes time to listen and explain treatment options thoroughly.

    Many express surprise at how different their experience was compared to traditional healthcare settings, noting that Dr. Bhatti treated them as partners in their care rather than just another appointment on a busy schedule. These genuine patient testimonials reflect what happens when a physician prioritizes patient wellbeing above all else, combining advanced medical expertise with authentic compassion and respect for each individual’s unique concerns and goals.

    Experience the Difference: Schedule Your Consultation

    Whether you’re suffering from prostate issues, chronic knee pain, uterine fibroids, or other conditions treatable through minimally invasive interventions, Dr. Bhatti offers the expertise, technology, and patient-centered approach you deserve.

    Contact Us:

    Location: 3300 Jimmy Johnson Blvd, Suite #130, Port Arthur, Texas 77642

    Phone: 409-213-9575

  • Comparing Fibroid Treatments: Why Minimally Invasive Options Are Changing the Game

    Comparing Fibroid Treatments: Why Minimally Invasive Options Are Changing the Game

    Not long ago, women with problematic fibroids faced a limited and often daunting set of treatment options: suffer through symptoms, undergo major surgery, or accept hysterectomy as the “final solution.” Today’s landscape looks dramatically different, with minimally invasive procedures offering effective relief without the risks and recovery time of traditional surgery.

    At Seamless Medical Centers, we’ve witnessed this evolution firsthand. Our patients often express amazement that they waited so long to seek treatment, not realizing that cutting edge solutions could address their symptoms with minimal disruption to their lives.

    The Traditional Treatment Landscape

    Historically, fibroid treatment followed a predictable progression:

    Watchful Waiting: Monitoring fibroids without active treatment

    Medical Management: Hormonal therapies to control symptoms

    Myomectomy: Surgical removal of fibroids while preserving the uterusHysterectomy: Complete removal of the uterus

    While these approaches remain valid for specific situations, they often involve significant limitations. According to the Fibroid Foundation, 300,000 women a year have hysterectomies due to uterine fibroids, representing a major surgical solution for what might be addressed less invasively.

    The Minimally Invasive Revolution

    Modern interventional radiology has transformed uterine fibroid treatment by offering procedures that are:

    • Less Invasive: Using small incisions or no incisions at all
    • More Precise: Targeting fibroids while preserving healthy tissue
    • Faster Recovery: Returning to normal activities within days, not weeks
    • Outpatient-Based: Going home the same day rather than hospital stays

    Detailed Treatment Comparison

    Traditional Open Myomectomy

    Approach: Large abdominal incision to remove fibroids

    Recovery: 4-6 weeks off work

    Hospital Stay: 2-3 days typically

    Risks: Higher infection risk, significant scarring, longer anesthesia exposure

    Laparoscopic/Robotic Myomectomy

    Approach: Multiple small incisions with specialized instruments

    Recovery: 2-3 weeks off work

    Hospital Stay: Usually same-day or overnight

    Advantages: Smaller scars, reduced pain compared to open surgery

    Hysterectomy

    Approach: Removal of entire uterus (various surgical approaches)

    Recovery: 6-8 weeks for full recovery

    Considerations: Permanent solution but eliminates future pregnancy possibility

    Impact: Significant life change requiring careful consideration

    Radiofrequency Ablation (RFA)

    Approach: Targeted thermal energy to destroy fibroid tissue

    Recovery: 3-5 days average return to work

    Hospital Stay: Outpatient procedure

    Precision: Treats fibroids while preserving healthy tissue

    Uterine Fibroid Embolization (UFE) – Our Specialty

    Approach: Blocking blood supply to fibroids through catheter in leg artery

    Recovery: About 1 week

    Performed by: Interventional radiologist

    Considerations: UFE has proven to be safe, versatile, and effective in reducing or eliminating symptoms related to uterine fibroids

    Why Minimally Invasive Matters

    The advantages of minimally invasive approaches extend beyond shorter recovery times:

    Reduced Complications: Smaller incisions mean lower infection risks and fewer surgical complications.

    Faster Healing: Less tissue trauma allows your body to heal more quickly and with less pain.

    Preserved Function: Maintaining uterine structure and function when possible offers long-term benefits.

    Cost Effectiveness: Shorter procedures, same-day discharge, and faster return to work reduce overall healthcare costs.

    Quality of Life: Minimal downtime means less disruption to work, family, and personal activities.

    Real-World Outcomes

    Research consistently demonstrates the effectiveness of modern minimally invasive approaches. Studies show UFE treatments were associated with fibroid volume reduction of 46.0% at 3 months and 65.4% at 12 months, with significant improvements in quality of life scores.

    Patient satisfaction rates for minimally invasive procedures consistently exceed those for traditional surgical approaches, largely due to the combination of effective symptom relief and reduced treatment burden.

    Choosing the Right Approach

    The best treatment depends on multiple factors:

    Fibroid Characteristics: Size, location, and number of fibroids influence treatment options

    Symptom Profile: Heavy bleeding, pressure symptoms, or pain may favor different approaches

    Personal Goals: Desire to preserve fertility, avoid surgery, or minimize recovery time

    Medical History: Previous surgeries, overall health, and other medical conditions

    Lifestyle Factors: Work demands, family responsibilities, and personal preferences

    Seamless Medical Centers Advantage

    Our focus on minimally invasive interventional radiology offers several key benefits:

    Expertise: Board-certified interventional radiologists with extensive experience in image-guided procedures

    Technology: State-of-the-art equipment and advanced imaging for optimal precision and safety

    Comprehensive Care: From initial consultation through follow-up, we support you throughout your treatment journey

    Insurance Coverage: Most major insurance plans cover our procedures, and we handle authorization processes

    Making an Informed Decision

    Choosing fibroid treatment is a personal decision that should be based on accurate, current information about all available options. Many women are surprised to learn about minimally invasive alternatives to traditional surgery.

    During your consultation, we’ll:

    • Review your specific fibroid characteristics
    • Discuss your symptoms and treatment goals
    • Explain all appropriate treatment options
    • Provide detailed information about what to expect
    • Answer all your questions thoroughly

    The Future Is Now

    The landscape of fibroid treatment continues to evolve, with new technologies and techniques constantly emerging. However, the fundamental shift toward minimally invasive, precision-based treatments represents a permanent change in how we approach this common condition.

    Ready to explore your options?

    Contact Seamless Medical Centers to learn how modern, minimally invasive treatments can address your fibroid symptoms effectively while minimizing disruption to your life. Your journey to better health starts with understanding your choices.

  • Infertility: Causes, Signs, Symptoms, & Treatments

    Infertility: Causes, Signs, Symptoms, & Treatments

    Infertility is a common medical condition that can also be deeply stressful and emotionally painful for individuals and couples.

    But you are not alone. It is more common than many people realize.

    According to the CDC, 1 in 5 (19%) of married women aged 15 to 49 in the U.S. with no prior births are unable to get pregnant after 1 year of trying.

    Studies suggest that after 1 year of having unprotected sex, 12% to 15% of couples are unable to conceive, and after 2 years, 10% of couples still have not had a live-born baby.

    Infertility is not only a “woman’s problem.”

    Causes may arise from the female side or from the male side.  Many couples have mixed or unexplained factors, which is why evaluating both partners is standard practice.

    Some causes of infertility are preventable. Medications or assisted reproductive technologies are aimed at maximizing the chances of conception.

    In this guide, you’ll gain an understanding of what infertility is, its types, causes, signs and symptoms, diagnoses, and available treatment options.

    What is Infertility?

    what is infertility

    According to the World Health Organization (WHO), infertility is a disease of the male or female reproductive system defined by the failure to achieve a pregnancy after 12 months or more of regular unprotected sexual intercourse.

    Conception requires a series of coordinated steps: a mature egg released during the ovulation portion of the menstrual cycle, sperm reaching and fertilizing the egg (typically in the fallopian tube), formation of an embryo, and successful embryo implantation in a receptive uterine lining.

    Disruption at any step, irregular or absent ovulation (menstrual cycle dysregulation), poor egg quality or reduced ovarian reserve, impaired sperm quality (count, shape, motility), tubal blockage, or uterine factors, can cause infertility.

    What are the Types of Infertility?

    Infertility affects millions of people and has an impact on their families and communities.

    WHO estimates suggest that approximately one in every six people of reproductive age worldwide experiences infertility in their lifetime.

    Types of infertility include:

    1. Primary Infertility

    This refers to a person or couple who have never achieved a pregnancy (or live birth) despite at least 12 months of regular, unprotected intercourse (or 6 months if the woman is 35 or older).

    Because no prior conception has occurred, the evaluation typically begins once the diagnostic threshold (12 or 6 months) is reached.

    Also, there is no prior successful pregnancy history; clinicians often consider a full infertility work-up (ovulation assessment, ovarian reserve, tubal/uterine imaging, semen analysis) more promptly.

    The absence of prior conception may suggest more significant or multiple contributing factors.

    2. Secondary Infertility

    It occurs when a person or couple has had at least one prior pregnancy (regardless of outcome) but is now unable to conceive after the defined interval of regular unprotected intercourse.

    Because a prior conception occurred, some systems (ovulatory, tubal, sperm) were once functional. The evaluation may focus on “what changed.”

    For example, age-related decline in ovarian reserve, new tubal damage, and a change in partner sperm quality.

    Therefore, prompt assessment is required, especially if age or other risk factors are present. Still, the perceived urgency is sometimes slightly less than in primary infertility (depending heavily on age and other context).

    3. Female-Factor Infertility

    This refers to cases in which the primary or sole contributing cause lies in the female partner’s reproductive system.

    For example, ovulatory dysfunction (irregular or absent ovulation), diminished ovarian reserve (reduced egg quantity/egg quality), tubal factor (blocked or damaged fallopian tubes), uterine or endometrial factors (uterine fibroids, endometriosis, poor endometrial receptivity).

    The clinician (often a reproductive endocrinologist) will assess menstrual cycle regulation, hormone levels (FSH, AMH), ovulation status, ovarian reserve, tubal patency, or uterine anatomy.

    Because female fertility declines with age (especially egg quality after age 35–40), the timeframe for intervention may be compressed, meaning earlier work-up and possibly earlier referral for assisted reproductive technologies may be indicated when diminished ovarian reserve or significant structural issues are found.

    4. Male-Factor Infertility

    This refers to infertility in which the male partner is the primary contributor. Common issues include reduced sperm quality (count, motility, morphology), sperm transport problems, hormonal/andrologic disorders.

    For this, evaluation begins with a partner’s semen analysis, hormonal testing (testosterone, FSH, LH), a physical/andrologic exam, and possibly imaging or genetic testing.

    Also, management may include lifestyle modifications, medical or surgical treatments (e.g., varicocele repair, hormonal therapy), and assisted reproduction when appropriate.

    If the male factor is severe, the timeline for moving to assisted reproductive technologies may be faster rather than prolonged expectant management.

    5. Tubal Infertility

    This is a specific female-factor category in which the fallopian tubes are blocked, scarred, or damaged, preventing the egg and sperm from meeting or the embryo from reaching the uterus.

    It’s often evaluated via imaging (hysterosalpingogram, sonohysterography, or laparoscopy).

    If tubal damage is significant (e.g., hydrosalpinx, bilateral obstruction), the timeline for moving to assisted reproduction (such as in vitro fertilization) may be accelerated because natural conception is unlikely.

    In some cases, surgical repair may be an option.

    6. Combined Infertility

    This category applies when both partners (female and male) have contributing fertility-limiting factors.

    For example, the female partner may have diminished ovarian reserve or tubal damage, and the male partner may have suboptimal sperm quality.

    Because two sets of problems exist, management often needs coordinated care involving both the reproductive endocrinologist and male fertility specialist (andrologist).

    Also, the timeline for intervention may be shorter given the combined burden, so clinicians often recommend more proactive assessment and treatment rather than “wait and see.”

    7. Unexplained Infertility

    This occurs when, after a standard infertility evaluation (including ovulation assessment, ovarian reserve testing, semen analysis, tubal and uterine imaging), no specific cause is identified.

    Even though no cause is found, treatment is still possible, but it’s empiric.

    Options may include ovulation induction, intrauterine insemination (IUI) timed to the fertile window, or more directly assisted reproductive technologies (ART), depending on age and other risk factors.

    Because there is no targetable cause, prognosis depends heavily on age, duration of infertility, and other subtle factors; timing becomes important, especially when the female partner is older.

    What Causes Infertility?

    what are the causes of infertility

    Many underlying medical, lifestyle, and environmental factors can impair egg quality, sperm quality, or the fertilisation/implantation sequence.

    The reasons for infertility vary from person to person. Here are the most common causes of infertility in women.

    Some reasons for female fertility problems include:

    • Ovulatory Disorders

    A normal menstrual cycle averages about 28 days; cycles that are fairly regular, roughly every 21 to 35 days, usually indicate that ovulation is occurring. Irregular or infrequent periods often mean ovulation is irregular or absent.

    When ovarian function is disrupted, a health-care provider should evaluate possible causes.

    Typical tests include follicle-stimulating hormone (FSH), anti-Müllerian hormone (AMH), and antral follicle count (AFC) on pelvic ultrasound.

    Common conditions that affect ovarian function

    • Polycystic ovary syndrome (PCOS): The most frequent cause of ovulatory infertility. PCOS disrupts the normal hormonal signals that trigger ovulation, causing irregular or absent ovulation and often associated metabolic and androgenic features.
    • Diminished ovarian reserve (DOR): Fewer eggs remain in the ovaries than expected for a woman’s age. DOR may be congenital, related to prior surgery or medical treatment, or unexplained; it reduces both the quantity and often the quality of eggs available for fertilization.
    • Hypothalamic or pituitary dysfunction: Research shows that problems in the brain’s reproductive control centers (the hypothalamus and pituitary) can alter the release of GnRH, LH, and FSH, impairing follicle development and ovulation.
    • Functional hypothalamic amenorrhea (FHA): A reversible condition caused by low body weight, rapid weight loss, excessive exercise, or significant stress. FHA suppresses GnRH secretion and stops or reduces ovulation.
    • Primary ovarian insufficiency (POI): Also called premature ovarian failure, POI occurs when the ovaries stop functioning before age 40. It’s characterized by irregular or absent periods, elevated FSH, and low estrogen, and may result in early loss of fertility.

    If ovarian dysfunction is suspected, timely evaluation and targeted testing help identify the specific cause and guide management, whether lifestyle changes, medical treatment to restore ovulation, or fertility-preserving or assisted-reproductive options.

    • Age-Related Decline

    As a woman ages, two key fertility-related processes deteriorate: the number of eggs remaining in her ovaries (often measured as ovarian reserve) and the ability of those eggs to fertilize and develop into healthy embryos (egg quality).

    Research shows that age-related changes in oocyte (egg) energy metabolism (for example, reduced ATP production, altered mitochondrial and lipid metabolism) degrade egg quality.

    Another study found that the prevalence of Diminished Ovarian Reserve (DOR) increased significantly with age, with more than double the rate in women over 30 compared to those under 30.

    Because both quantity and quality decline with age, the “fertile window” shrinks in both monthly opportunities and cumulative chances.

    • Tubal Issues

    When the tubes are damaged, blocked, scarred, or their epithelial lining is compromised, the egg and sperm cannot meet properly, or the resulting embryo cannot travel safely to the uterus. This condition is known as tubal factor infertility (TFI).

    Causes of fallopian tube damage or blockage can include:

    • Blockage or scarring: Infections trigger inflammation that leads to adhesions, scar tissue, or complete tubal occlusion, preventing the egg and sperm from meeting.
    • Epithelial damage: The ciliated cells of the fallopian tube help transport the fertilised egg into the uterus. Damage to these cells slows or stops embryo transit.
    • Ectopic risk: Because the embryo’s path is compromised, implantation may occur in the tube itself rather than the uterus, leading to ectopic pregnancy.

    One retrospective cohort of 2,892 women with tubal infertility found that those with prior ectopic pregnancy had worse outcomes in IVF/ICSI cycles.

    Because tubal damage is often irreversible, prompt identification can shift management earlier to assisted reproductive technologies (ART) rather than prolonged natural-cycle attempts.

    • Endometriosis

    Endometriosis is the presence of endometrial-like tissue outside the uterus (for example, on the ovaries, fallopian tubes, or pelvic peritoneum).

    This aberrant tissue can cause inflammation, adhesions (scar tissue), hormonal dysregulation, and altered pelvic anatomy. These changes can impact fertility by:

    • Impairing ovulation or reducing egg/follicle quality when the ovary is involved (e.g., endometrioma).
    • Causing tubal/peritoneal adhesions that interfere with the meeting of egg and sperm or embryo transport.
    • Altering the uterine lining (endometrium) so that embryo implantation is less likely.
    • Creating a hostile, inflammatory environment in the pelvis may reduce fertility potential.

    A study found that women with endometriosis exhibit endometrial changes (hormonal imbalances, immune dysregulation, altered microRNA/gene expression) that reduce the likelihood of successful implantation.

    Another research report found that, among women with endometriosis, oxidative stress, dysregulated steroidogenesis (via aromatase P450), and elevated cytokines (IL-6, IL-8, TNF-α) were identified as factors likely impairing follicle/oocyte development and thus fertility.

    • Uterine Factors

    Uterine-factor infertility refers to conditions in the uterus that interfere with one or more steps of conception, implantation, or maintenance of a pregnancy.

    These include anatomical abnormalities and acquired lesions that alter the uterine cavity, lining, or musculature.

    A cross-sectional study found a high prevalence of acquired uterine anomalies (polyps, submucosal fibroids) and congenital anomalies (septate, bicornuate uteri) among sub-fertile women.

    Because these uterine issues affect the “plumbing and lining” part of the reproductive system, the cavity where the embryo must implant, timely detection and repair can often improve chances of conception.

    • Thyroid Disease

    According to the American Thyroid Association, one in eight women will develop a thyroid disorder in her lifetime.

    Thyroid problems usually fall into two main types:

    • Hyperthyroidism (overactive thyroid): The gland makes too much thyroid hormone.
    • Hypothyroidism (underactive thyroid): The gland does not produce enough thyroid hormone.

    Some people may also develop thyroid nodules, which are small lumps or growths in the thyroid. Most nodules are harmless, but in some cases, they can cause hormonal changes or make swallowing uncomfortable.

    Research shows that overt (clinical) hypothyroidism is consistently associated with menstrual irregularities, anovulation, luteal-phase defects, and reduced conception rates. Treating overt hypothyroidism (levothyroxine) typically restores regular cycles and improves chances of conceiving.

    Another research from the National Institutes of Health (NIH) also highlights that about 2–4% of women of reproductive age have hypothyroidism.

    This condition can interfere with normal ovulation and disrupt menstrual cycles, which may lead to infertility. Hypothyroidism can appear on its own, develop after pregnancy, or occur following treatment for an overactive thyroid. In some cases, it may also be present from birth.

    • Autoimmune Disorders

    Autoimmune diseases develop when the immune system mistakenly targets the body’s own healthy cells, leading to ongoing inflammation and tissue damage. This heightened immune response can impact fertility in several ways.

    A large population-based study analyzed over 568,000 births and discovered that women with untreated infertility were 25% more likely to develop conditions such as lupus, Sjögren’s syndrome, or inflammatory myopathies within nine years after delivery.

    Also, the research indicates that infertility itself may act as an early warning sign for underlying autoimmune dysfunction, even when a pregnancy is achieved naturally.

    Autoimmune disorders can affect fertility in several ways:

    • Hormonal disruptions: Some autoimmune conditions can damage hormone-producing glands, leading to irregular periods and ovulation issues.
    • Chronic inflammation: Ongoing inflammation may affect egg quality, embryo development, and the uterus’s ability to accept an embryo.
    • Auto-antibodies: In conditions like antiphospholipid syndrome, antibodies can interfere with blood flow to the uterus and placenta, increasing the risk of miscarriage.
    • Medication effects: Certain immunosuppressants used to treat autoimmune diseases may temporarily reduce fertility or affect ovarian function.
    • Higher miscarriage risk: Women with autoimmune disorders, especially lupus and antiphospholipid syndrome, have a greater chance of pregnancy loss.

    Overall, autoimmune activity, inflammation, and treatment effects can all contribute to fertility challenges.

    • Chronic Medical Conditions

    Long-term illnesses such as diabetes, hypertension, autoimmune disorders, kidney disease, and untreated thyroid problems can disrupt the delicate hormonal balance needed for ovulation and healthy menstrual cycles.

    These conditions may also affect blood flow to reproductive organs, increase inflammation, or lead to complications like irregular periods, poor egg quality, or difficulty maintaining a pregnancy.

    For example, research shows that chronic metabolic disorders such as obesity and metabolic syndrome impair fertility by disrupting the hypothalamic–pituitary–ovarian (HPO) axis, lowering oocyte quality, and reducing implantation and live-birth rates; multiple recent reviews document these mechanisms and worse assisted reproduction outcomes in obese women.

    Another research indicates that decreased ovarian reserve, altered ovarian function, and worse clinical pregnancy rates in women with diabetes.

    • Lifestyle Factors

    Unhealthy habits such as smoking, excessive alcohol use, poor diet, and lack of exercise can disrupt the hormonal balance required for ovulation and regular menstrual cycles.

    Moreover, exposure to environmental toxins, like pesticides, plastics (BPA), and certain chemicals, may also damage eggs and sperm or affect implantation.

    Plus, poor sleep, chronic dehydration, and overuse of caffeine further strain the body’s hormonal regulation.

    What are the Signs of Infertility?

    what are the signs of infertility

    Infertility in people who menstruate is often first suspected from objective clues in the reproductive history, physical exam, or simple tests.

    Many of these signs point to hormonal or structural problems that can impair ovulation, egg quality, tubal function, or uterine receptivity.

    The common signs of infertility include:

    • Irregular menstrual cycles: Cycles shorter than 21 days, longer than 35 days, or unpredictable, often a sign of ovulatory problems like PCOS or hormonal imbalance.
    • Very heavy or very light periods: Abnormal flow can signal fibroids, polyps, hormonal disorders, or uterine lining problems that affect implantation.
    • Absence of ovulation: No ovulation confirmed by tests (like low mid-luteal progesterone). Seen in PCOS, thyroid issues, hyperprolactinemia, or POI.
    • History of pelvic inflammatory disease (PID) or STIs: Documented infections such as chlamydia or gonorrhea increase the risk of tubal scarring and blocked fallopian tubes.
    • Recurrent miscarriages (2 or more): Repeated pregnancy loss may indicate uterine abnormalities, genetic issues, autoimmune disorders, or hormonal imbalance.
    • Abnormal vaginal discharge (infection-related): Clinically confirmed infections can travel upward and damage the tubes, affecting fertility.
    • Persistent pelvic pain: Exam-related or recorded chronic pelvic pain may be a sign of endometriosis or pelvic adhesions that interfere with conception.

    What are the Symptoms of Infertility

    what are the symptoms of infertility

    While infertility itself often has no symptoms, many women experience physical changes that point to an underlying condition affecting their reproductive health.

    Common symptoms linked to infertility include:

    • Painful periods (dysmenorrhea): Severe cramping may indicate endometriosis or pelvic inflammation.
    • Pain during intercourse (dyspareunia): Often linked to endometriosis, pelvic adhesions, or chronic inflammation.
    • Chronic pelvic pain: Persistent pain outside menstruation may reflect endometriosis, fibroids, or pelvic scarring.
    • Hot flashes or night sweats: A sign of low estrogen and possible premature ovarian insufficiency (POI).
    • Nipple discharge (galactorrhea): Can indicate hyperprolactinemia, which disrupts ovulation.
    • Rapid weight gain: Frequently associated with insulin resistance or hormonal imbalance, especially in PCOS.
    • Acne or excessive facial hair (hirsutism): Signs of androgen excess are often seen in PCOS and other ovulatory disorders.

    How Is Infertility Diagnosed?

    No single test can detect every cause of infertility, and many tests miss mild problems.

    A comprehensive approach typically includes:

    Detailed Medical History and Physical Exam

    Your clinician reviews your menstrual cycle, past pregnancies, infections, surgeries, medications, lifestyle factors, and overall health.

    A pelvic exam checks for fibroids, ovarian masses, or signs of endometriosis. This guides which tests come next.

    Basic Ovulation Testing (Is ovulation occurring?)

    Home ovulation kits detect the LH surge and help time intercourse.

    Also, a mid-luteal progesterone test is performed ~7 days before your period to confirm ovulation. Low levels suggest absent or irregular ovulation.

    Ovarian-Reserve Testing (How many eggs remain/ovarian activity)

    It typically includes three key measures:

    • AMH (anti-Müllerian hormone): A blood test that can be done any time in the cycle and provides an estimate of ovarian reserve.
    • FSH and estradiol: Usually measured on cycle day 2–4; an elevated FSH or abnormal estradiol can indicate reduced reserve.
    • Antral follicle count (AFC): A transvaginal ultrasound performed early in the cycle counts small follicles and gives a visual estimate of ovarian reserve.

    Transvaginal ultrasound (TVUS) (structural and functional imaging)

    A transvaginal ultrasound evaluates the uterus and ovaries: it detects fibroids, ovarian cysts or endometriomas, and helps assess the antral follicle count.

    It’s a routine, non-invasive test used throughout the diagnostic workup.

    Tests of Tubal Patency

    To check whether eggs and sperm meet, the following tests are done:

    • Hysterosalpingography (HSG): X-ray with contrast to see if the fallopian tubes are open.
    • Saline infusion sonohysterogram (SIS): ultrasound with saline to detect polyps, fibroids, or adhesions in the uterine cavity.

    Diagnostic Laparoscopy (Selected cases)

    A laparoscopy is a minimally invasive surgery (small incisions, camera into the pelvis) reserved for specific indications: suspected endometriosis not visible on imaging, persistent pelvic pain, or unclear tubal disease after HSG/other tests.

    It can both diagnose and, in some cases, treat adhesions or endometriosis.

    Remember, the testing protocols vary between providers, so it is reasonable to seek a second opinion if you’re unsure about results or next steps.

    Infertility Treatment Options: From Least Invasive to Most Advanced

    infertility treatment options

    Infertility treatments vary in complexity and invasiveness, ranging from lifestyle changes to advanced assisted reproductive technologies (ART). Also, they are tailored to age, diagnosis, and reproductive goals.

    Here are some of the most commonly used infertility treatment options:

    Lifestyle Changes

    Optimizing overall health can naturally improve fertility. This includes achieving a healthy weight, eating a balanced diet, quitting smoking, limiting alcohol, managing stress, and avoiding endocrine-disrupting chemicals.

    Even modest lifestyle adjustments can improve ovulation, egg quality, sperm quality, and endometrial receptivity.

    Ovulation Induction Medications

    For women with ovulatory dysfunction (such as PCOS or hormonal imbalance), medications stimulate ovulation:

    • Clomiphene citrate: Oral medication that induces ovulation.
    • Letrozole: An aromatase inhibitor often preferred for women with PCOS.
    • Gonadotropins: Injectable hormones for more controlled ovarian stimulation.

    Hormonal regulation may also include correcting thyroid, prolactin, or luteal-phase deficiencies.

    Intrauterine Insemination (IUI)

    IUI involves placing washed sperm directly into the uterus around the conception window to increase the chances of fertilization.

    Often combined with ovulation induction. Suitable for mild male factor infertility, unexplained infertility, or cervical issues.

    In Vitro Fertilization (IVF)

    IVF is an ART procedure where eggs are retrieved from the ovaries, fertilized with sperm in a lab, and the resulting embryos are cultured to the blastocyst stage for transfer.

    Embryo grading helps select the best embryos for transfer, maximizing success rates. IVF is used for tubal ligation factor, severe male infertility, or when IUI has failed.

    Intracytoplasmic Sperm Injection (ICSI)

    A specialized form of IVF where a single sperm is injected directly into an egg. Often used for severe male infertility, low sperm count, poor motility, or previous fertilization failure in IVF.

    Donor Gametes

    When a woman’s eggs are of poor quality, or a man has no viable sperm, donor eggs or sperm can be used. This allows fertilization with donor genetic material.

    This is often recommended for women over 40 or for couples where male infertility is severe. Donor eggs have a higher success rate in older women.

    Gestational Surrogacy

    Gestational surrogacy involves another woman carrying a pregnancy for a couple who cannot conceive or carry a pregnancy themselves. The embryo is created through IVF using the eggs and sperm from the intended parents or donors.

    It is typically used when a woman cannot carry a pregnancy due to health conditions or failed IVF cycles.

    Fertility Preservation (Egg/Embryo Freezing)

    Fertility preservation includes freezing eggs or embryos for future use. This is often done by women who wish to delay childbearing for personal or medical reasons, such as cancer treatment.

    Common for women over 35 who want to delay childbearing, or for those facing medical treatments that may affect fertility.

    However, for men, sperm freezing is an option before undergoing treatments like chemotherapy.

    Choosing the right treatment requires a personalized evaluation by a reproductive endocrinologist or fertility specialist, taking into account age, diagnosis, and prior response to therapy.

    Complications of Infertility Treatment

    Infertility treatments, especially those involving hormonal stimulation or assisted reproduction, carry some risks, though serious problems are relatively rare.

    Here are some complications of infertility treatment:

    Ovarian Hyperstimulation Syndrome (OHSS)

    OHSS occurs when the ovaries over-respond to stimulation, causing fluid leakage, ovarian swelling, and sometimes more severe effects.

    A recent large review estimated that moderate to severe OHSS affects 1–5% of IVF cycles. Severe OHSS can lead to complications such as hemoconcentration, clotting risk, and more.

    Multiple Pregnancy Risk

    Fertility treatments (especially when more than one embryo is transferred, or with strong ovulation stimulation) increase the likelihood of twins or higher-order multiples.

    Also, multiple gestations are a major contributor to pregnancy complications after fertility treatment. Studies show that many of the excess risks (preterm birth, cesarean section, preeclampsia) are mediated by having multiples.

    Ectopic Pregnancy

    Although relatively uncommon, ectopic pregnancy (when an embryo implants outside the uterus) can occur following fertility treatment.

    Research shows that ectopic pregnancies have been observed as one of the more serious adverse events, especially in protocols involving embryo transfer.

    Emotional Stress, Anxiety, Depression

    The emotional toll of infertility treatments can be significant, leading to increased stress, anxiety, and depression.

    The uncertainty of treatment outcomes, coupled with hormonal changes, can exacerbate these feelings.

    For this, support from counselors, support groups, and a strong partner relationship can help alleviate emotional distress.

    Procedure-Related Discomfort

    Some infertility treatments, particularly egg retrieval and sperm collection procedures, may cause temporary discomfort or pain.

    These procedures are generally quick and performed under sedation or local anesthesia, ensuring patient comfort.

    Financial and Insurance Considerations

    Infertility treatments can be expensive, and not all insurance plans cover the full cost.

    This financial burden can add stress to the process, but many fertility clinics offer payment plans, and some regions have specific fertility treatment insurance coverage.

    Medication Side Effects

    Fertility drugs (gonadotropins, hCG trigger, etc.) can cause side effects like bloating, nausea, mood changes, and fluid shifts.

    Because some protocols involve high doses of hormones, the body’s response can be quite variable, which is why close monitoring is essential.

    While there are potential complications associated with infertility treatments, most are rare and manageable with appropriate medical supervision.

    To address these, open communication with healthcare providers and proper monitoring significantly reduce the chances of severe complications.

    How to Prevent Infertility?

    While not all cases of infertility are preventable, many risk factors are modifiable, and taking proactive steps to address these factors can improve your chances of maintaining fertility.

    Here are some practical ways to reduce your risk:

    • Maintain a Healthy BMI: A healthy weight supports regular menstrual cycles and ovulation.
    • Quit Smoking: Smoking affects egg quality in women and sperm in men, reducing fertility.
    • Limit Alcohol Intake: Excess alcohol can disrupt hormone production and ovulation.
    • Use STI Protection: Condoms and regular screenings can prevent infections that damage reproductive organs.
    • Treat Infections Promptly: Prompt treatment of infections such as pelvic inflammatory disease (PID) prevents fertility issues.
    • Manage Thyroid Disease: Regular monitoring and treatment of thyroid issues support fertility.
    • Control Chronic Conditions: Managing diabetes and autoimmune disorders reduces their impact on fertility.
    • Reduce Toxin Exposure: Limiting exposure to BPA and pesticides protects reproductive health.
    • Get Regular Well-Woman Exams: Regular exams help detect fertility issues early.
    • Track Menstrual Cycles: Monitoring your cycle helps identify irregularities that may affect fertility.

    By taking these steps, individuals can improve their reproductive health and increase their chances of conception.

    Frequently Asked Questions (FAQs)

    Why am I not getting pregnant?

    Not getting pregnant can be frustrating, but it is often related to a combination of factors involving both partners. Several factors can affect fertility:

    • Ovulation Issues: Irregular ovulation can prevent conception. Tracking ovulation can help identify this issue.
    • Male-Factor Infertility: Low sperm count or poor motility can impact fertility. A semen analysis can identify sperm issues.
    • Age: As you age, egg quality and quantity decline, reducing the chances of pregnancy.
    • Timing: Conception is most likely when intercourse happens close to ovulation.
    • Underlying Conditions: Conditions like thyroid disorders or diabetes can affect fertility.

    How to know if you’re infertile?

    You may consider a fertility evaluation if you haven’t conceived after 12 months of trying (<35 years) or 6 months (≥35 years). Earlier assessment is recommended for signs like irregular periods, missed ovulation (anovulation), recurrent miscarriages, or known reproductive conditions. Tests often include cycle monitoring, ovulation tracking, and AMH testing to assess ovarian reserve and guide next steps.

    How common is infertility?

    Infertility affects a significant number of couples in the U.S. According to the CDC, about 19% of married women aged 15–49 with no prior births are unable to get pregnant after one year of trying. Delays in childbearing (women starting families later) and demographic shifts contribute to this trend.

    Is infertility genetic?

    Yes, genetics can play a role in certain infertility conditions. Some women may inherit risks for endometriosis, premature ovarian insufficiency (POI), or polycystic ovary syndrome (PCOS), while men can inherit Y-chromosome deletions or Klinefelter syndrome, affecting sperm production. Therefore, a family history of reproductive issues can signal a higher risk. Couples concerned about hereditary infertility may benefit from genetic counseling to understand risks and testing options.

    Can infertility be cured?

    Some infertility causes are treatable; for example, hormonal imbalances can be managed with medications, ovulation issues may improve with lifestyle changes, and structural problems like fibroids or tubal blockages can sometimes be corrected surgically. Other cases may not be fully “curable” but can be managed effectively with assisted reproductive technologies (ART) such as IVF. Success depends on the underlying cause, age, and overall reproductive health.

    Conclusion

    Infertility is a common medical condition, affecting nearly 1 in 5 women of reproductive age in the U.S., and often involves factors from both partners.

    Causes range from ovulation disorders, tubal or uterine issues, and age-related egg decline to male-factor infertility, including low sperm count or genetic conditions.

    Many signs, such as irregular cycles, recurrent miscarriages, or difficulty conceiving despite regular intercourse, can signal the need for evaluation. Plus, symptoms like painful periods or hormonal changes may indicate underlying disorders.

    The good news is that most infertility causes are treatable or manageable. Lifestyle changes, ovulation induction, hormonal therapy, surgical correction, or advanced ART procedures like IVF and ICSI can significantly improve the chance of conception.

    While the journey can be emotionally challenging, understanding the causes, monitoring cycles, and accessing appropriate care empowers couples.

    Infertility is not a reflection of personal failure, and with timely support and evidence-based treatment, many individuals and couples achieve successful pregnancy outcomes. Your fertility matters, and help is available.

  • Uterine Fibroids: Types, Causes, Symptoms, Diagnosis, & Treatments

    Uterine Fibroids: Types, Causes, Symptoms, Diagnosis, & Treatments

    Uterine fibroids (also called leiomyomas) are benign tumours made of smooth muscle and fibrous tissue that form in or on the muscular wall of the uterus.

    It can range in size from as small as a pea or as large as a grapefruit.

    Epidemiological analyses estimate that 40–80 % of people with a uterus have fibroids, with the greatest prevalence between 30 to 50 years.

    Despite being non‑malignant, fibroids can severely affect quality of life by causing heavy menstrual bleeding, chronic pelvic pain, pressure symptoms, infertility, or pregnancy complications.

    Moreover, new survey data from The Harris Poll for the Society of Interventional Radiology show that many women still have misunderstandings about their treatment options.

    In fact, 17% believe a hysterectomy, the complete removal of the uterus, is the only solution, including 27% of women aged 18–34. However, minimally invasive treatments like UFE, in addition to surgical treatment, are a great option.

    This article explains uterine fibroids, including their types, causes, symptoms, complications, and treatment options.

    What are Uterine Fibroids?

    what are uterine fibroids

    Uterine fibroids are non-cancerous (benign) growths that develop in the wall of the uterus. They are made of smooth muscle cells and fibrous (connective) tissue. Fibroids can be as small as a pea or as large as a grapefruit, and a woman may have one fibroid or many.

    Most fibroids grow slowly or not at all. Fibroids are usually described by where they grow:

    • Submucosal
    • Intramural
    • Subserosal

    Each fibroid’s size and location influence the symptoms a person may have and which treatments are appropriate.

    Who Usually Develops Uterine Fibroids?

    Fibroids are most common in women of reproductive age, particularly between about 30 and 50 years old. The risk increases with age during the childbearing years and then generally decreases after menopause.

    Evidence from epidemiological and mechanistic research identifies several modifiable and non‑modifiable risk factors:

    Risk FactorEvidences
    Race/ethnicityResearch shows that black women are about three times more likely to develop fibroids than the general population, often experiencing earlier onset, larger fibroids, and more severe symptoms such as pelvic pain, menopause, bladder problems, and heavy bleeding.
    Genetic predispositionHaving close relatives with fibroids increases the risk, with genetic predisposition playing a significant role.
    Age, early menarche & late menopauseFibroids are rare before puberty; incidence peaks in the 40s and declines after menopause. Early menarche and late menopause prolong estrogen exposure and increase risk.
    Obesity and high BMIA nutritional review shows that obesity increases aromatase activity, converting androgens to estrogens, which stimulate fibroid growth.
    HypertensionA longitudinal analysis of 2,570 midlife women found that untreated hypertension was associated with a 19 % higher risk of incident fibroids, whereas antihypertensive medication reduced risk by 37 %. Participants who developed hypertension during follow‑up had a 45 % increased risk.
    NulliparityWomen who have not delivered children have a higher risk. Pregnancy may be protective because uterine remodelling during pregnancy may reduce the number of uterine stem cells.
    Hormonal factorsA study highlights that prolonged exposure to estrogen and progesterone stimulates growth; fibroids enlarge during pregnancy and shrink after menopause.
    Vitamin D deficiencyLow vitamin D levels increase risk; supplementation may inhibit fibroid growth.
    Environmental factorsResearch indicates diets high in red meat, saturated fats, and alcohol, exposure to endocrine‑disrupting chemicals (e.g., organophosphate esters, plasticizers), tobacco use, and vitamin D deficiency have been associated with increased risk.
    Genitourinary microbiome & inflammationAlterations in the reproductive tract microbiome and chronic low‑grade inflammation may promote fibroid growth.

    3 Types of Uterine Fibroids

    Fibroids are classified according to their location in the uterus and relationship to the uterine wall.

    The most commonly used system is the International Federation of Gynecology and Obstetrics (FIGO) classification. For clinical purposes, three broad types are usually discussed:

    1. Submucosal Fibroids

    Grow just beneath the uterine lining and can protrude into the uterine cavity. They’re the type most likely to cause heavy or prolonged menstrual bleeding and fertility problems because they distort the lining where an embryo would implant.

    2. Intramural Fibroids

    Form inside the muscular wall of the uterus and are the most common type. They can make the uterus feel larger, cause pelvic pain or pressure, and may contribute to heavy bleeding and fertility issues, depending on size and exact location.

    3. Subserosal Fibroids

    Develop on the outer surface of the uterus and grow outward. These usually cause bulk-related symptoms, such as pelvic pressure, pain, or urinary/bowel problems, from pressing on nearby organs. Some subserosal fibroids are pedunculated (stalked) and can cause acute pain if they twist.

    Clinical Note: The fibroid’s location strongly affects symptoms and treatment choices. For example, submucosal fibroids are often removed hysteroscopically to improve bleeding or fertility, while large intramural or subserosal fibroids may need other surgical or radiologic approaches.

    What Causes Uterine Fibroids?

    what are the causes of uterine fibroids

    The exact cause of fibroid development is still unclear, but several mechanisms are implicated:

    • Hormonal Imbalance

    Estrogen and progesterone promote the proliferation of smooth muscle cells and the extracellular matrix in fibroids. Fibroids contain more estrogen and progesterone receptors than normal myometrium.

    Hormone fluctuations explain why fibroids grow during pregnancy and shrink after menopause.

    • Genetic and Molecular Alterations

    Somatic mutations in the MED12 gene are the most common driver mutation, detected in 45–90% of fibroids. Other genes can also be involved. These changes make the cells grow more than they should.

    • Growth Factors and Vascular Regulation

    Fibroids produce growth factors (e.g., transforming growth factor‑β and vascular endothelial growth factor) and exhibit altered angiogenic signalling, leading to increased vascularisation and fibroid growth.

    • Environmental and Inflammatory Triggers

    Vitamin D deficiency, endocrine‑disrupting chemicals, chronic inflammation, and obesity contribute to pathogenesis by altering hormone metabolism and extracellular matrix deposition.

    What are the Symptoms of Uterine Fibroids?

    what are the symptoms of uterine fibroids

    Symptoms depend on the size, number, and location of fibroids; many women are asymptomatic.

    The most common symptoms include:

    • Heavy or Prolonged Menstrual Bleeding (Menorrhagia)

    Submucosal fibroids, which grow close to the uterine lining, are the most likely to cause heavy, long, or irregular periods. This type of bleeding can be severe enough to lead to iron-deficiency anemia, causing fatigue, weakness, or shortness of breath.

    • Pelvic Pain or Pressure

    Larger intramural or subserosal fibroids can press on nearby organs. This pressure may cause:

    • Low back pain
    • A swollen or enlarged abdomen
    • Urinary frequency or difficulty emptying the bladder
    • Constipation or discomfort during bowel movements

    These symptoms are caused by the fibroid pushing against the bladder, bowel, or pelvic nerves.

    • Reproductive and Fertility Issues

    Fibroids can affect fertility by changing the shape of the uterus, blocking the fallopian tubes, or interfering with embryo implantation. They may also increase the risk of miscarriage.

    Studies show fibroids are found more in women seeking fertility treatment, and both the number and size of fibroids are directly linked to how severe symptoms are and how much they impact quality of life.

    • Pregnancy Complications

    During pregnancy, fibroids can increase the risk of:

    • Difficulty becoming pregnant
    • Preterm birth
    • Breech presentation
    • Heavy bleeding after delivery (postpartum hemorrhage)

    The risk depends heavily on the fibroid’s location and size. Some fibroids remain stable during pregnancy, while others may grow due to higher hormone levels.

    What are the Risk Factors for Uterine Fibroids?

    Several factors can increase a woman’s chances of developing uterine fibroids:

    • Family history: Women with a mother or sister who had fibroids are more likely to develop them.
    • Age (30–50 years): Fibroids usually appear and grow during the reproductive years, especially in the 30s and 40s, then often shrink after menopause.
    • Obesity and high blood pressure: Higher body weight and hypertension are both linked to a greater risk of fibroids.
    • Lifestyle factors: Low physical activity, a diet high in red meat, and low intake of fruits and vegetables may contribute to fibroid growth.
    • Early menstruation and late menopause: Starting periods at a young age and going through menopause later in life expose the uterus to hormones for longer, increasing the chance of developing fibroids.

    What are the Complications of Uterine Fibroids?

    Besides the symptoms listed above, fibroids can lead to specific complications:

    • Anemia from Heavy Bleeding

    When fibroids, especially those near the uterine lining, cause heavy or prolonged periods, chronic blood loss can lead to iron-deficiency anemia. This may require iron supplements or other medical treatment to restore iron levels.

    • Infertility and Adverse Pregnancy Outcomes

    A study shows that large submucosal fibroids (those that grow into the uterine cavity) are linked with infertility and a higher risk of miscarriage and preterm birth.

    For selected patients, removing submucosal fibroids with hysteroscopic myomectomy has been shown to improve reproductive outcomes. However, the benefit depends on the fibroid type and individual factors.

    • Urinary and Bowel Dysfunction

    Fibroids that press on the bladder or rectum can cause urinary frequency, urgency, difficulty emptying the bladder, or constipation and discomfort during bowel movements.

    These “bulk” effects come from the fibroid’s size and location rather than bleeding.

    Malignant transformation of a fibroid into a leiomyosarcoma is extremely rare. Because the risk is small but clinically important, doctors evaluate rapidly growing or suspicious masses carefully.

    How are Uterine Fibroids Diagnosed?

    Evaluation begins with a clinical history and pelvic examination. The choice of test depends on symptoms, suspected fibroid location, and whether fertility is a concern.

    Initial Assessment

    • Pelvic Exam: A doctor may feel an enlarged or irregular uterus during a routine pelvic exam, which can suggest the presence of fibroids.
    • Medical History and Symptoms: Information about heavy bleeding, pelvic pain, or urinary problems helps guide which tests are needed.

    Imaging Tests

    • Pelvic Ultrasound (first-line test): Ultrasound is the most common and readily accessible modality for detecting fibroids. It shows their size, number, and basic location.
    • Magnetic Resonance Imaging (MRI): MRI provides detailed fibroid mapping and is useful for surgical planning or when ultrasound results are inconclusive.
    • CT Scan: CT is not routinely used to diagnose fibroids, but it may show them incidentally if performed for another reason.

    Procedures for Uterine Cavity Assessment

    • Hysteroscopy or Hysterosalpingography: Hysteroscopy allows direct visualisation and treatment of submucosal fibroids. Hysterosalpingography helps evaluate intracavitary lesions.
    • Laparoscopy: Used when other imaging is inconclusive or when concomitant pelvic pathology is suspected.

    Additional Tests

    • Blood Tests: These help check for anemia from heavy bleeding and rule out other causes of symptoms.

    Uterine Fibroids Treatment Options

    uterine fibroids treatment options

    Uterine treatment decisions depend on fibroid size, location, symptom severity, patient age, and fertility desires. Many small or asymptomatic fibroids can be monitored (“watchful waiting”).

    Symptomatic fibroids may require medical therapy, minimally invasive procedures, or surgery.

    Here are some options supported by recent evidence and guideline recommendations.

    Medical Management

    • Symptom Control

    Symptom control is the goal of medical therapy; medications generally do not eradicate fibroids but can reduce bleeding and shrink tumours.

    According to the American College of Radiology’s Appropriateness Criteria, first‑line agents include oral contraceptive pills and progestin‑containing intrauterine devices, which reduce bleeding symptoms.

    Non‑hormonal alternatives such as tranexamic acid are effective for heavy menstrual bleeding.

    • GnRH Agonists and Antagonists

    Two types of medicines can shrink fibroids and reduce symptoms: GnRH agonists (such as leuprolide) and GnRH antagonists (such as elagolix, linzagolix, and relugolix).

    Research shows that these medicines work by lowering estrogen levels, which in turn causes fibroids to shrink. Because low estrogen can cause side effects such as hot flashes and bone thinning, they are usually used for a short time, often to shrink fibroids before surgery.

    Newer treatments combine a low dose of estrogen and progestin with the medication. This helps prevent strong side effects while still controlling heavy menstrual bleeding, and this approach is FDA-approved.

    • Selective Progesterone Receptor Modulators (SPRMs)

    Drugs such as ulipristal acetate reduce bleeding and fibroid size, but concerns about hepatotoxicity have limited widespread use.

    Other Agents: NSAIDs relieve pain; combined oral contraceptives, progestin injections or implants, and the levonorgestrel intrauterine device control bleeding. Iron supplementation addresses anemia.

    Minimally Invasive Procedures

    • Uterine Fibroid Embolization (UFE)

    Uterine fibroid embolization is a catheter‑based procedure performed by Dr. Zagum Bhatti, a board-certified interventional radiologist.

    A catheter is introduced through the femoral or radial artery and navigated into the uterine arteries; small embolic particles occlude the branches supplying the fibroids, causing ischemic necrosis and shrinkage.

    Randomised trials show that UFE provides symptom relief comparable to myomectomy; quality‑of‑life scores and re‑intervention rates at four years are not significantly different. Advantages include a shorter hospital stay, lower risk of blood transfusion, and faster recovery.

    However, patients may experience post‑embolization syndrome (pelvic pain, fever, nausea) and expulsion of submucosal fibroids.

    Another retrospective study of 155 patients undergoing UFE for submucosal fibroids found that UFE reduced the median volume of the dominant fibroid by 64% and achieved >90% devascularization in 94.8% of cases.

    High patient satisfaction was reported, with 84.5% discharged without further intervention.

    Severe adverse events were rare (3.2 %), while mild adverse events (mainly infection or vaginal discharge) occurred in 16.8 %. These findings support UFE as an effective and safe option for submucosal fibroids.

    • Radiofrequency Ablation (RFA)

    RFA (available as laparoscopic Acessa or transcervical Sonata systems) uses thermal energy to coagulate fibroid tissue.

    Under ultrasound guidance, a needle electrode delivers radiofrequency energy, heating the fibroid to ~100 °C and causing coagulative necrosis, which is gradually reabsorbed. RFA is typically a day surgery and preserves the uterine wall structure.

    • MRI‑Guided Focused Ultrasound (MRgFUS/HIFU)

    MRgFUS uses high‑intensity focused ultrasound waves to thermally ablate fibroid tissue under MRI guidance. Advantages include no incisions, minimal blood loss, and rapid recovery.

    According to the ACR Appropriateness Criteria, complications are rare but can include skin burns, nerve injury, and deep vein thrombosis.

    Compared with UFE, MRgFUS has longer procedure times and higher re‑intervention rates.

    Surgical Options

    • Myomectomy (Uterine‑Sparing Surgery)

    Myomectomy removes fibroids while preserving the uterus and fertility. It can be performed hysteroscopically (for submucosal fibroids), laparoscopically/robotically, or via open abdominal surgery.

    • Hysterectomy

    Hysterectomy (removal of the uterus) provides definitive treatment with no risk of recurrence, making it appropriate for women who do not desire future fertility.

    Options include total hysterectomy (uterus and cervix removed), supracervical hysterectomy (uterus only), and may be performed vaginally, laparoscopically, or abdominally.

    Frequently Asked Questions (FAQs)

    Are Uterine fibroids common?

    Yes. About 40–80% of people with a uterus develop fibroids, with the highest prevalence between ages 30 and 50. Most fibroids are small and cause no symptoms, so many people only find out about them during a pelvic exam or ultrasound.

    Do uterine fibroids cause pain?

    Many women experience pelvic pressure or pain; symptoms depend on fibroid size and location. Submucosal fibroids often cause heavy bleeding, while large intramural or subserosal fibroids can cause back pain, urinary frequency, and constipation.

    Can uterine fibroids be cancerous?

    Fibroids are almost always benign. Malignant transformation into leiomyosarcoma (cancer) is extremely rare.

    What size of uterine fibroids should be removed?

    There is no single size threshold. Indications include significant symptoms (heavy bleeding, pain, infertility), rapid growth, or distortion of the uterine cavity. Fibroids causing heavy bleeding often warrant intervention.

    Can uterine fibroids cause bleeding?

    Yes. Heavy menstrual bleeding is one of the most common symptoms and can lead to iron‑deficiency anemia. Iron supplementation or treatment to reduce bleeding may be necessary.

    Can uterine fibroids cause anemia?

    Yes, uterine fibroids can lead to anemia. This happens when heavy or prolonged menstrual bleeding caused by fibroids depletes the body’s iron stores, which are essential for making red blood cells. Over time, this can lead to a low red blood cell count, resulting in fatigue, weakness, and other anemia-related symptoms.

    Can I get pregnant with uterine fibroids?

    Yes, you can get pregnant with a uterine fibroid, but it can sometimes affect fertility or pregnancy depending on its size, number, and location. Submucosal fibroids, which grow into the uterine cavity, are most likely to interfere with embryo implantation or increase the risk of miscarriage. Large intramural fibroids within the uterine wall can also reduce fertility or cause complications, while subserosal fibroids on the outer surface usually do not affect fertility but may cause discomfort if very large. Doctors may recommend monitoring, medication, or surgical removal for fibroids that could interfere with conception or a healthy pregnancy.

    Do uterine fibroids go away on their own?

    Uterine fibroids usually do not disappear on their own, but their growth often slows or stops after menopause when hormone levels (estrogen and progesterone) decline. Some small fibroids may remain stable for years without causing symptoms, so not all fibroids require treatment. Doctors often monitor fibroids that aren’t causing problems and only recommend intervention if they grow, cause symptoms, or affect fertility.

    Can uterine fibroids be prevented?

    No, uterine fibroids cannot always be prevented. However, certain lifestyle choices may help reduce the risk or slow their growth. Maintaining a healthy weight, exercising regularly, eating a balanced diet rich in fruits, vegetables, and fiber, controlling blood pressure, getting enough vitamin D, limiting alcohol and red meat, and using certain hormonal contraceptives may all help. While these steps don’t guarantee prevention, they can support overall uterine health and may reduce the chances of fibroids developing or growing quickly.

  • Genicular Artery Embolization: Revolutionary Knee Pain Treatment Without Surgery

    Genicular Artery Embolization: Revolutionary Knee Pain Treatment Without Surgery

    If you’ve been struggling with persistent knee pain from osteoarthritis, you’re not alone. Adults aged 45 and older who experience knee osteoarthritis often find limited relief from traditional treatments like medications, physical therapy, or injections. While many eventually face the prospect of knee replacement surgery, a revolutionary alternative is changing the treatment landscape: Genicular Artery Embolization (GAE).

    GAE offers a minimally invasive path to lasting knee pain relief without the risks, lengthy recovery, and surgical trauma associated with traditional knee surgery. This breakthrough procedure is helping patients reclaim their mobility and quality of life through an outpatient treatment that takes just a few hours.

    What Is Genicular Artery Embolization?

    Genicular Artery Embolization is a minimally invasive procedure that treats chronic knee pain caused by osteoarthritis by reducing abnormal blood flow and inflammation in the knee joint. Unlike surgery that replaces or removes damaged joint tissue, GAE addresses the issues that cause osteoarthritis pain: synovial inflammation and abnormal blood vessel growth.

    How GAE Works

    Genicular Artery Embolization (GAE) is a minimally invasive procedure that targets one of the key sources of osteoarthritis pain — inflammation in the knee joint lining. When osteoarthritis develops, the synovial membrane (the soft tissue that lines the joint) can become inflamed and grow abnormal new blood vessels and pain-sensing nerves. These changes feed ongoing inflammation and increase pain sensitivity.

    During the GAE procedure, an interventional radiologist makes a tiny incision, usually in the groin or wrist, and inserts a thin catheter into the bloodstream. Using advanced X-ray imaging, the doctor carefully guides the catheter to the genicular arteries, which supply blood to the knee joint. Once in position, microscopic embolic particles are gently released into these arteries. These particles block the abnormal small vessels that sustain inflammation in the joint. By reducing excess blood flow and calming pain-sensitive nerves, GAE helps decrease swelling and relieve pain.

    The result is lasting pain reduction and improved knee function — all without removing any bone, cartilage, or healthy tissue.

    The Benefits of GAE for Knee Osteoarthritis

    Proven Pain Relief

    Genicular Artery Embolization (GAE) has been shown in clinical studies to deliver lasting relief from knee pain and significant improvements in quality of life. Approximately 70-80% of patients experience significant pain reduction and improved function. Many patients report being able to walk longer distances, stay active, and return to their daily routines with greater comfort. Sleep quality often improves as nighttime pain decreases, and overall joint stiffness and inflammation are noticeably reduced.

    GAE offers an effective, minimally invasive option for those seeking relief from chronic knee pain without surgery.

    Minimally Invasive with Rapid Recovery

    Unlike knee replacement surgery that requires large incisions, extended hospital stays, and months of rehabilitation, GAE is performed as an outpatient procedure. Most patients return home the same day with only a small bandage covering the catheter insertion site. Recovery is remarkably quick—many patients resume normal activities within one to two weeks, compared to the three to six months typically required after knee replacement.

    No General Anesthesia Required

    GAE is performed under moderate sedation, eliminating the risks associated with general anesthesia. This makes the procedure accessible to patients who might be considered high-risk surgical candidates due to age or other medical conditions like heart disease or diabetes.

    Long-Lasting Results

    Research shows that GAE provides sustained pain relief extending from 1-3 years or longer for many patients. For patients seeking to delay or avoid knee replacement surgery, GAE offers a durable solution that can provide years of improved function and quality of life.

    Who Is a Candidate for GAE?

    Genicular Artery Embolization (GAE) may be an excellent option for individuals seeking relief from chronic knee pain caused by osteoarthritis — especially when other treatments haven’t provided lasting results.

    You may be a good candidate if you:

    Have mild to moderate knee osteoarthritis (Kellgren–Lawrence grade 2–3)Experience persistent knee pain despite conservative treatmentsHave not found adequate relief from physical therapy, anti-inflammatory medications, or cortisone injectionsWish to avoid or delay knee replacement surgeryAre not a surgical candidate due to other medical conditionsHave preserved joint structure but ongoing pain from inflammation

    Patients with more advanced osteoarthritis can still experience benefits from GAE, though outcomes are often more durable in earlier stages of the disease.

    During your consultation, an interventional radiologist will review your imaging studies and medical history to determine whether GAE is the most appropriate treatment for your condition.

    The GAE Procedure: What to Expect

    Before Your Procedure

    Your interventional radiologist will review your medical history, current medications, and imaging studies. You’ll receive detailed instructions about preparing for the procedure, including when to stop eating and drinking. Blood tests may be ordered to ensure your body can safely process the contrast dye used during imaging.

    During the Procedure

    On the day of your treatment, you’ll receive moderate sedation to keep you comfortable but awake. The interventional radiologist will numb the access site (typically your groin or wrist) and make a tiny puncture to insert the catheter. Using real-time X-ray guidance, the catheter is advanced to the genicular arteries supplying your knee.

    Contrast dye is injected to visualize the blood vessels and identify the abnormal vessels contributing to your pain. Once identified, embolization material is carefully delivered through the catheter to block these vessels. The entire procedure typically takes one to two hours.

    After the Procedure

    Following the GAE procedure, you’ll rest in a recovery area for several hours while medical staff monitor you. Most patients experience minimal discomfort and are discharged home the same day with specific care instructions. You’ll be advised to avoid strenuous activities for a few days, but most people can walk immediately after the procedure.

    Recovery and Results Timeline

    Pain relief from GAE typically begins within one to two weeks as inflammation in the knee joint subsides. Many patients notice gradual, continued improvement over the following two to three months. During this time, the abnormal blood vessels remain blocked while your body’s normal circulation adapts to maintain healthy knee tissue.

    You can expect to return to work within a few days, depending on your job’s physical demands. Low-impact activities like walking can usually resume almost immediately, while higher-impact activities may need to wait a few weeks. Your interventional radiologist will provide personalized guidance based on your recovery progress.

    Experience GAE at Seamless Medical Centers

    At Seamless Medical Centers in Port Arthur, TX, Dr. Zagum Bhatti and our team of board-certified interventional radiologists specialize in providing life-changing, minimally invasive procedures like Genicular Artery Embolization. Dr. Bhatti’s patient-first philosophy means we’re committed to helping you understand all your treatment options—even if that means recommending a procedure we don’t offer, because your health and wellbeing come first.

    We understand that chronic knee pain significantly impacts every aspect of your life—from limiting your favorite activities to affecting your independence and overall well-being. GAE offers hope for those who thought surgery was their only option, providing an effective, minimally invasive alternative that can restore your quality of life with less pain, fewer risks, and faster recovery times.

    Most insurance plans, including Medicare and Medicaid, cover medically necessary procedures like GAE. We’ll work with your insurance provider to verify coverage and obtain pre-authorization before scheduling your treatment.

    If you’re tired of living with knee pain and want to explore whether GAE is right for you, we invite you to schedule a consultation with our team. We’ll thoroughly evaluate your condition, answer all your questions, and ensure you fully understand your options.

    Contact Seamless Medical Centers Today

    Ready to explore minimally invasive solutions for your knee pain?Phone: 409-213-9575Address: 3300 Jimmy Johnson Blvd, Suite #130, Port Arthur, Texas 77642

    Call us or book your consultation online to learn how Genicular Artery Embolization can help you return to the activities you love—the seamless way.